Practical Outpatient Algorithms 9 rapid decision pathways for nephrology & general medicine
Designed for GPs and IM residents managing common renal and metabolic problems in the outpatient setting. Each algorithm distills current KDIGO, ACC/AHA, and local DOH guidance into actionable decision steps.
W Rivero, MD, FPCP, DPSNLast reviewed: May 2026Internal Medicine · Nephrology
Clinical use only. These algorithms are decision-support tools for licensed practitioners. They do not replace clinical judgement, complete history-taking, or appropriate specialist referral. Always individualise management to the patient.
9 rapid decision algorithms at a glance — edema workup through metabolic acidosis correction. Each pathway distills KDIGO 2024, ACC/AHA (American Heart Association), and local DOH (Department of Health) guidance into outpatient-ready clinical steps.
1
Outpatient Edema Workup
Bilateral pitting edema is among the most common outpatient presentations. Identify the mechanism before prescribing diuretics.
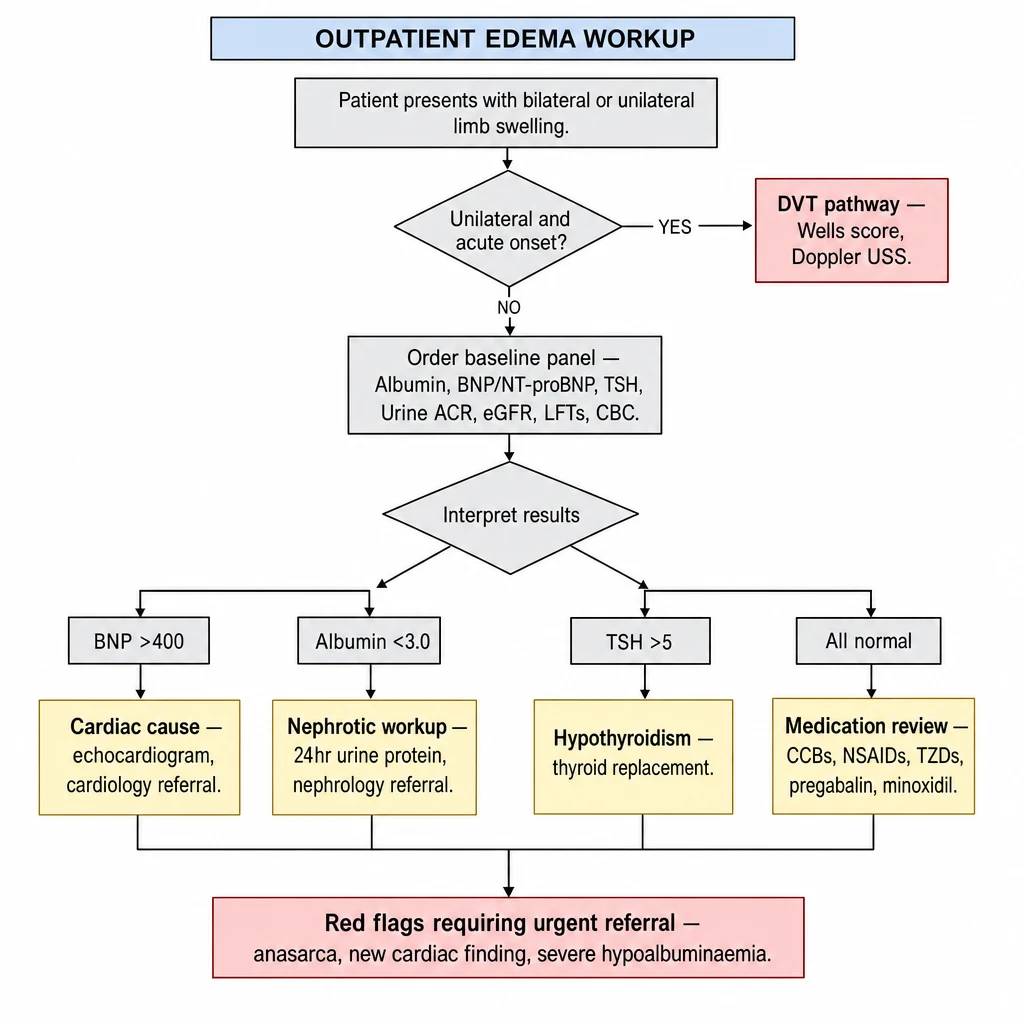
Algorithm 1 overview — Edema Workup. Begin with unilateral vs bilateral; order the targeted panel (BNP, albumin, TSH, ACR, eGFR); branch to cardiac, nephrotic, thyroid, or drug-induced cause. Anasarca or new cardiac finding = urgent referral.
Trigger
Patient presents with limb swelling or weight gain
First characterise: pitting vs non-pitting · unilateral vs bilateral · acute (<72 h) vs chronic · distribution (ankle only / below knee / anasarca)
Decision
Is the edema unilateral and acute?
Yes → DVT until proven otherwise
Apply Wells DVT score. If ≥2 points or high clinical suspicion → bilateral compression Doppler USS same day. If negative and score low → consider cellulitis, Baker's cyst ruptured, compartment syndrome, lymphedema (non-pitting, rubbery).
No → Bilateral / Chronic → Continue below
Bilateral edema almost always has a systemic cause. Proceed with mechanism-based workup.
Cardiac cause likely. Request echo. Refer cardiology if new finding. Optimise loop diuretic (furosemide). Check electrolytes and renal function.
Albumin < 3.0 g/dL
Hypoalbuminaemia. Check urine protein (nephrotic if >3.5 g/day). Check LFTs for cirrhosis. Check total protein + SPEP if myeloma suspected. → Refer nephrology if nephrotic range.
TSH > 5 mIU/L
Hypothyroid edema. Classic non-pitting myxedema. Start levothyroxine; edema resolves with euthyroid state over weeks.
Decision
All labs normal — is the patient on any of these medications?
Withdraw or switch offending agent. CCB-induced edema: switch to ARB (angiotensin receptor blocker) + thiazide combination. Monitor for resolution over 2–4 weeks.
No → Venous insufficiency
Most common in chronic bilateral ankle edema without systemic cause. Confirm with venous duplex. Manage: compression stockings, leg elevation, sodium restriction.
Admit If
Red flags requiring urgent escalation
Anasarca with albumin <2.0 g/dL · BNP >1,000 (acute decompensated HF) · O₂ saturation <94% at rest · Creatinine acutely rising · BP >180/120 with edema · New ascites with altered sensorium (hepatic encephalopathy)
Tip: Amlodipine is the most missed cause in the Philippines — always check CCB use first
2
Hyperkalemia Management
Outpatient-focused. Any K⁺ ≥ 6.0 mEq/L requires an ECG (electrocardiogram) before a management decision. Type IV RTA (hyporeninaemic hypoaldosteronism) is the most common cause in CKD/DKD (diabetic kidney disease) outpatients.
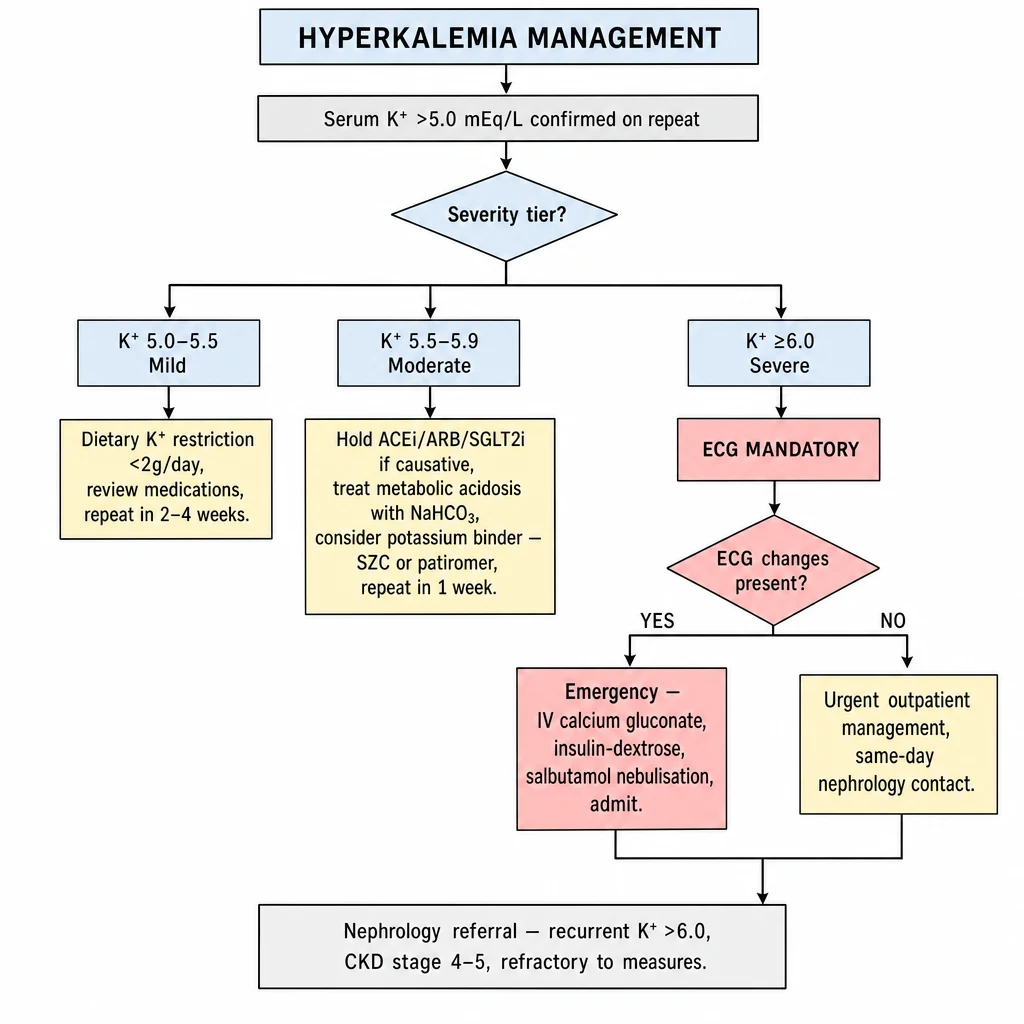
Algorithm 2 overview — Hyperkalemia Management. Classify by severity: Mild 5.0–5.5, Moderate 5.5–5.9, Severe ≥6.0 with mandatory ECG. Outpatient steps: dietary K⁺ restriction, hold offending agents, treat acidosis, consider patiromer or SZC. K⁺ ≥6.0 + ECG changes = emergency.
Trigger
Serum K⁺ above 5.0 mEq/L on routine labs
Rule out pseudohyperkalaemia first: haemolysed sample · prolonged transport (>2 h) · extreme leukocytosis or thrombocytosis (WBC >100,000 or plt >1,000,000) · fist clenching during draw. Repeat if clinical picture doesn't match.
Decision
What is the confirmed K⁺ level?
Level
Severity
Immediate Step
5.0–5.4 mEq/L
Mild
Dietary review + medication audit. Recheck in 2–4 weeks.
5.5–6.0 mEq/L
Moderate
ECG. Dietary restriction. Consider potassium binder. Reduce/hold RAASi if appropriate.
> 6.0 mEq/L
Severe
ECG immediately. If any ECG changes → ADMIT. If ECG normal and patient asymptomatic → may manage outpatient with close follow-up.
Outpatient management steps (mild–moderate, no ECG changes)
1. Dietary restriction
Target <40 mEq/day (≈ 1,500 mg K⁺)
Avoid: saging (banana), abokado (avocado), kamote, mongo, coconut water
Leaching technique for vegetables (peel, cut, boil in large water, discard water)
2. Medication review
ACEi (angiotensin-converting enzyme inhibitor) / ARB reduce dose or switch if K⁺ >5.5 with CKD
NSAIDs stop — reduce aldosterone activity
TMP-SMX stop — blocks ENaC like amiloride
K-sparing diuretics hold spironolactone if K⁺ >5.5
Loop diuretics increase dose if volume overloaded
Action
Potassium binders — when and which
Use if K⁺ persistently >5.5 mEq/L despite dietary restriction and medication optimisation, especially when RAASi continuation is clinically important (CKD progression, heart failure).
Sodium zirconium cyclosilicate (SZC / Lokelma): 10 g TID × 48 h (acute), then 5–10 g QD maintenance. Onset 1 h. Preferred in Philippines (available). Raises serum HCO₃ slightly — beneficial in CKD acidosis. Patiromer (Veltassa): 8.4 g QD with food. Onset 7–12 h. Not interchangeable with SZC. Use away from other medications (chelates). Limited availability in PH. Sodium polystyrene sulphonate (Kayexalate): older agent; avoid in ileus risk; PO or enema. Still widely used in PH due to cost.
Action
Treat contributing metabolic acidosis
Metabolic acidosis shifts K⁺ extracellularly (↑ K⁺ by ~0.6 mEq/L per 0.1 unit ↓ in pH). Correcting HCO₃ to ≥22 mEq/L with oral sodium bicarbonate (see Algorithm 9) reduces K⁺ by 0.3–0.6 mEq/L in CKD patients — often sufficient for mild hyperkalaemia.
Refer
Nephrology referral criteria for hyperkalaemia
K⁺ persistently >5.5 despite maximal outpatient therapy · Recurrent admissions for severe hyperkalaemia · K⁺ >5.5 with eGFR <30 (needs CKD co-management) · Suspected type IV RTA requiring diagnostic workup (renin, aldosterone levels)
Type IV RTA: low renin + low aldosterone; K⁺ 5.0–6.0; mild NAGMA; eGFR 30–60; DKD most common cause
RAAS (renin–angiotensin–aldosterone system) inhibitors: necessary for cardio-renal protection — do not stop without binder trial first
Recheck K⁺ within 1–2 weeks after any intervention
If on SZC: recheck K⁺ in 48–72 h during loading phase
Avoid raw/unprocessed bananas, kamote leaves, and coconut water in dialysis patients
3
Hyponatremia Management
Serum Na⁺ <135 mEq/L. Classify by osmolality first, then volume status. The correction rate is as important as the target — overcorrection causes osmotic demyelination syndrome (ODS).
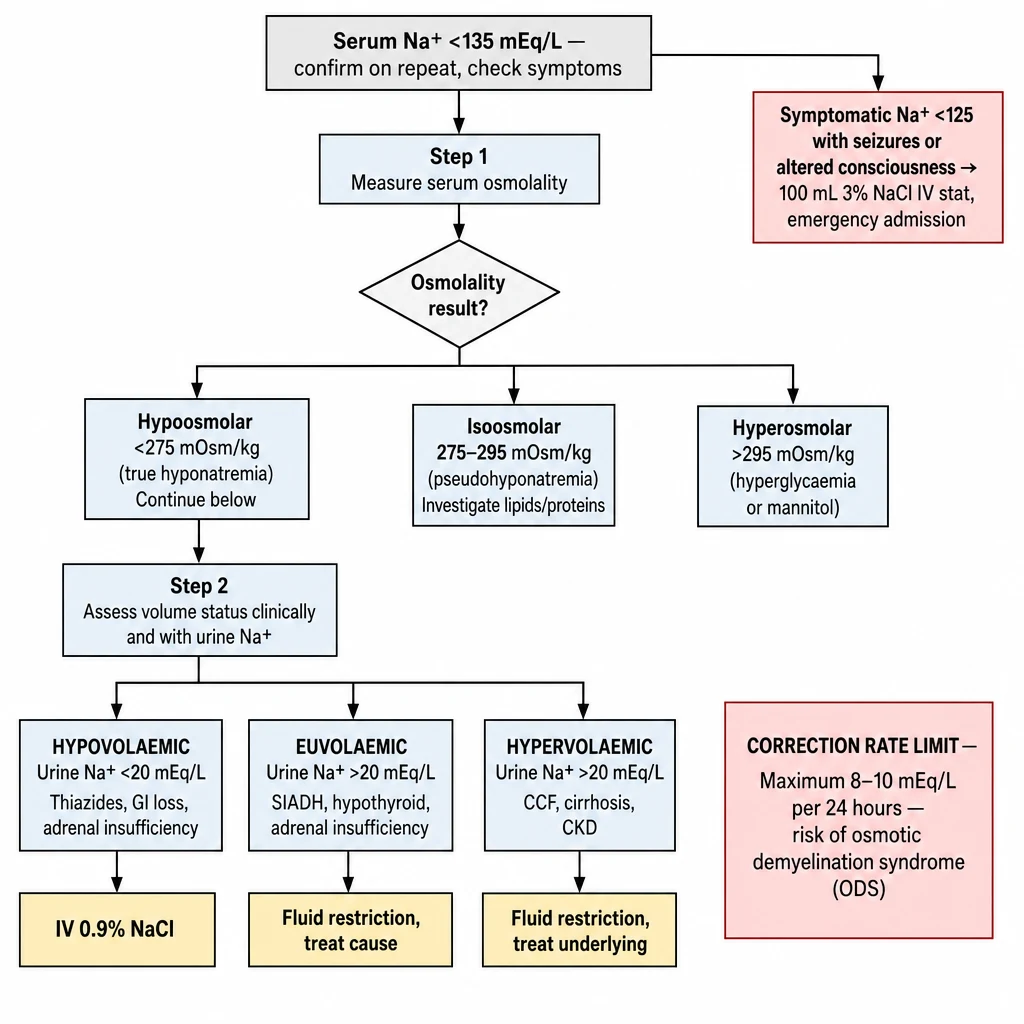
Algorithm 3 overview — Hyponatremia Management. Step 1: serum osmolality (hypoosmolar / isoosmolar / hyperosmolar). Step 2: volume status (hypovolaemic → SIADH → hypervolaemic). Step 3: correction rate — max 8–10 mEq/L per 24h to prevent ODS. Symptomatic Na⁺ <125 = 100 mL 3% NaCl bolus.
Trigger
Serum Na⁺ <135 mEq/L found on labs
Assess symptoms: asymptomatic vs mild (nausea, headache) vs moderate (vomiting, confusion) vs severe (seizures, coma, respiratory arrest). Symptomatic hyponatraemia → hospital.
Decision
Step 1: Measure serum osmolality
Osm >290 mOsm/kg (Hypertonic)
Translocational hyponatraemia. Hyperglycaemia most common. Correct Na⁺ by +1.6 mEq/L per 100 mg/dL glucose above 100. Treat glucose — Na⁺ normalises.
Osm 280–290 mOsm/kg (Isotonic)
Pseudohyponatraemia. Extreme hyperlipidaemia or hyperproteinaemia. Measure Na⁺ on blood gas analyser (direct ISE). No treatment of Na⁺ needed.
Osm <280 mOsm/kg (Hypotonic)
True hyponatraemia. Proceed to Step 2: assess volume status.
Decision
Step 2: Assess volume status (clinical + urine studies)
Treatment: Fluid restriction 800–1,000 mL/day. Salt tabs. If refractory: tolvaptan (V2-receptor antagonist) — specialist-initiated only.
Hypervolaemic (edematous)
edema + ascites present
Causes: CHF, cirrhosis, nephrotic syndrome
Urine Na typically <20 (effective arterial volume depletion despite edema)
Treatment: Fluid restriction + treat underlying cause. Loop diuretic if CHF. Do not give saline.
Warning
Correction rate limits — the most important rule
Chronic hyponatraemia (>48 h or unknown duration): Maximum correction = 8–10 mEq/L per 24 hours · 18 mEq/L per 48 hours.
Faster correction → Osmotic demyelination syndrome (ODS): central pontine myelinolysis. Dysarthria, dysphagia, quadriparesis, locked-in syndrome. Irreversible. High-risk for ODS: Alcohol use disorder · malnutrition · hypokalaemia · baseline Na⁺ <120 mEq/L · liver disease. Acute hyponatraemia (<48 h): Can correct at 1–2 mEq/L/h initially until symptoms resolve (usually +5 mEq/L sufficient for seizures/coma).
Admit If
Symptomatic or severe hyponatraemia
Seizures, coma, obtundation, vomiting with aspiration risk → ADMIT immediately. Emergency: 3% NaCl 150 mL IV over 20 min → repeat ×2 if no improvement → target +5 mEq/L in first hour → reassess. Stop 3% NaCl once symptomatic improvement or Na⁺ reaches 130 mEq/L.
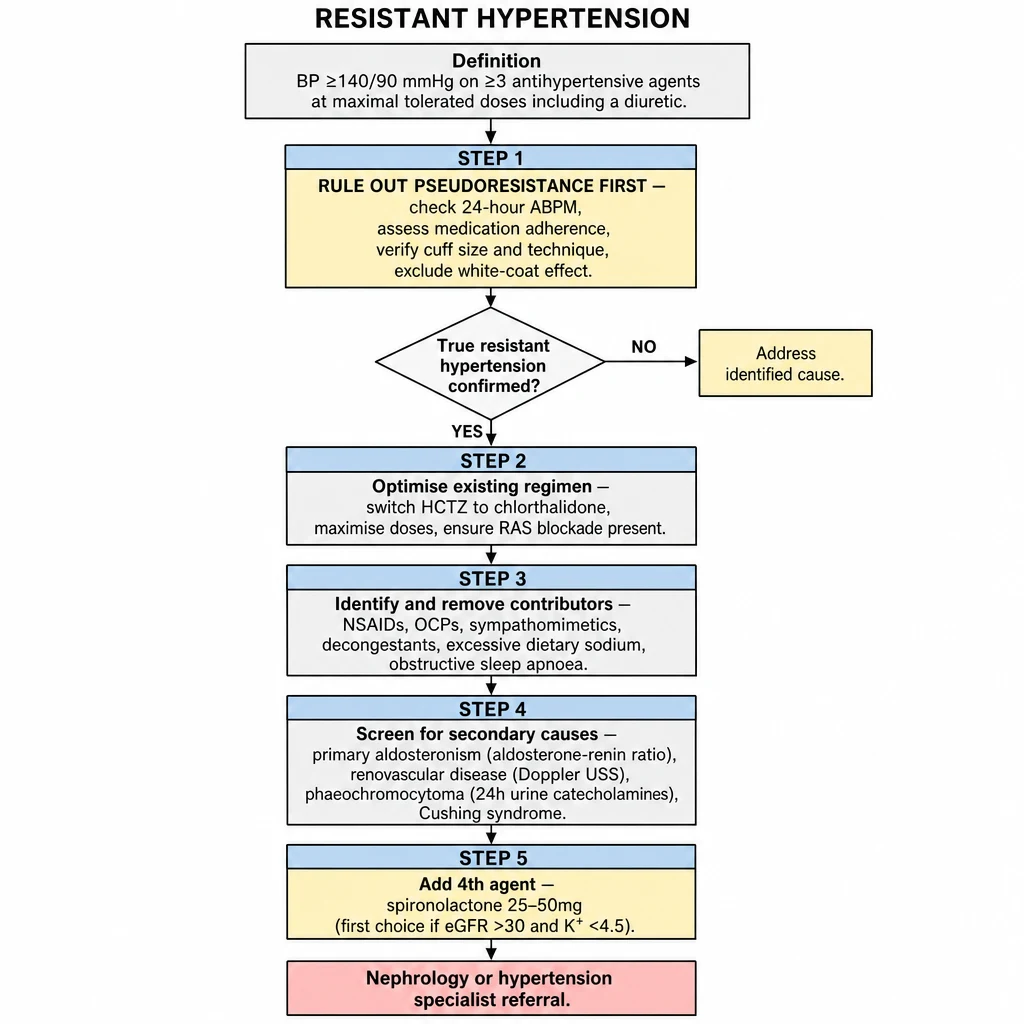
BP ≥ 140/90 mmHg on ≥ 3 maximally tolerated antihypertensive agents from different classes, including a diuretic. Pseudoresistance is far more common than true resistant hypertension — rule it out first.
Clinic BP ≥ 140/90 on ≥ 3 antihypertensives at adequate doses
Includes patients on ≥ 4 drugs with controlled BP (controlled resistant HTN). This accounts for ~10–20% of treated hypertensives.
Decision
Step 1: Rule out pseudoresistance — the most important step
Measurement errors
Wrong cuff size (most common) — use large cuff for arm circumference >33 cm
Talking, crossing legs, unsupported arm during measurement
Measure after 5 min rest in seated position
Check both arms — use higher reading arm
White-coat / Non-adherence
White-coat HTN: Home BP monitoring (HBPM) target <135/85 mmHg at home. ABPM gold standard (daytime avg <135/85).
Non-adherence: Pill count, pharmacy records, directly observed dosing, urine drug screen for antihypertensives (thiazide metabolite).
Suboptimal doses or inappropriate drug combinations (two ARBs, two CCBs)
Action
Step 2: Optimise current regimen before adding agents
Essential questions:
(1) Is a diuretic included? Thiazide (HCTZ/chlorthalidone) for eGFR ≥30; loop diuretic (furosemide BID) if eGFR <30 or fluid overload.
(2) Are drugs at maximum tolerated doses?
(3) Are doses timed correctly? Evening dosing of one agent improves nocturnal dipping.
(4) Single-pill combinations improve adherence — preferred where available in PH.
Action
Step 3: Identify and eliminate lifestyle and drug contributors
First choice: Spironolactone 25–50 mg daily (PATHWAY-2 trial: most effective 4th agent; reduces SBP ~8–9 mmHg vs placebo). Check K⁺ and eGFR at 4 weeks. Avoid if K⁺ >5.0 or eGFR <30. If spironolactone not tolerated (gynaecomastia, hyperkalaemia):
Eplerenone 25–50 mg (more selective, less anti-androgenic) · Doxazosin 4–8 mg (α-blocker) · Bisoprolol 5–10 mg if not on BB · Moxonidine (central α-agonist, but inferior evidence). Avoid clonidine (rebound hypertension on missed doses — dangerous in outpatient use).
Refer
When to refer to nephrology or hypertension specialist
BP uncontrolled after 4-drug regimen + lifestyle + adherence confirmed · Confirmed secondary cause (aldosteronism, RAS) · eGFR <45 with resistant HTN (likely CKD-driven; needs nephrology co-management) · Consider renal denervation evaluation at tertiary centres
4-Drug Sequence for Resistant HTN (after pseudoresistance excluded)
Step 1: RAS blocker (ACEi or ARB) + CCB (amlodipine) + Thiazide (chlorthalidone preferred over HCTZ) — maximise all doses
Step 2: Add loop diuretic if eGFR <30 or edema present (switch thiazide to furosemide BID)
Step 4: Add doxazosin or bisoprolol based on patient profile · Refer if still uncontrolled
5
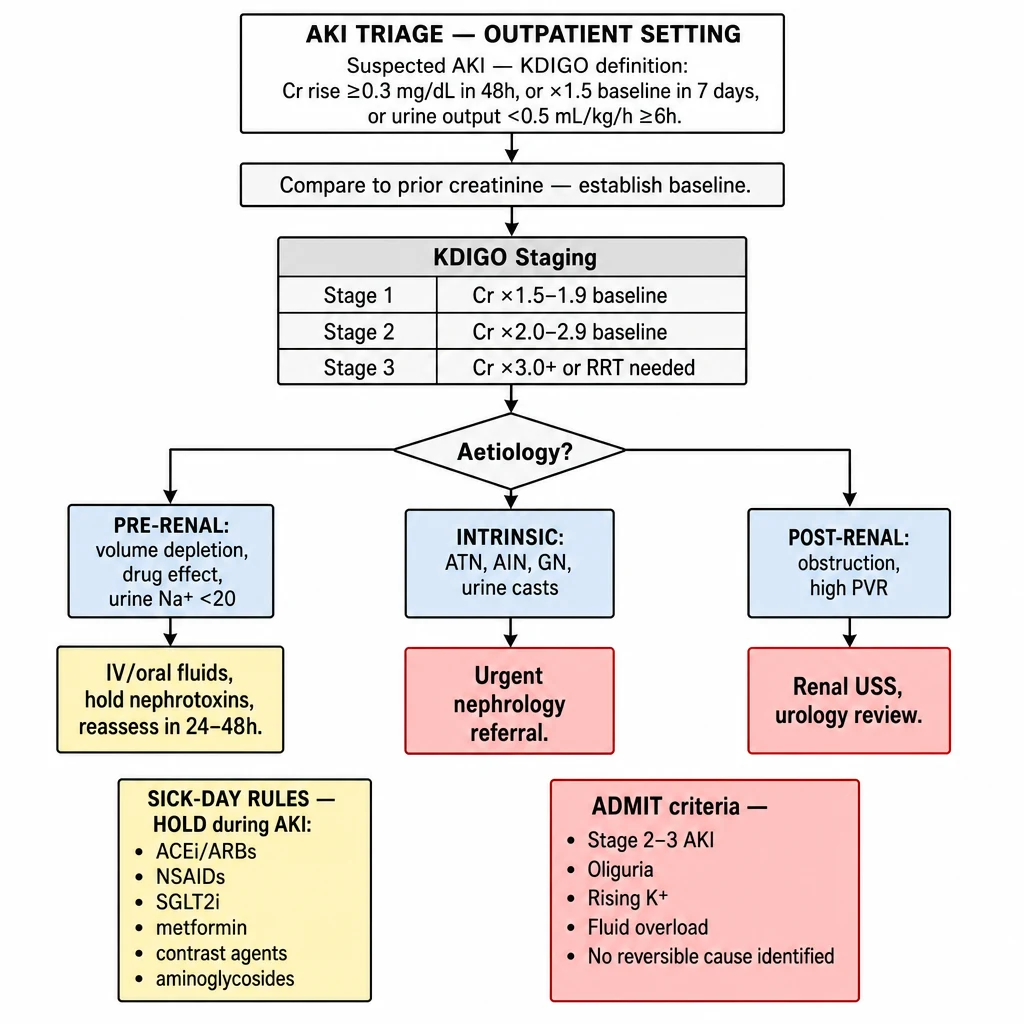
AKI Triage — Outpatient Setting
Acute Kidney Injury (KDIGO): rise in serum creatinine ≥0.3 mg/dL within 48 h, or ×1.5 baseline within 7 days, or urine output <0.5 mL/kg/h for ≥6 h. Always compare to a prior creatinine — do not assume baseline from a single elevated value.
Acutely elevated creatinine or oliguria on outpatient visit
First: retrieve previous creatinine. Check eHR, prior labs, old results from other facilities. A creatinine of 2.0 mg/dL may be AKI (if baseline 0.8) or chronic CKD (if stable for 2 years). This distinction drives everything.
Decision
Classify AKI severity (KDIGO staging)
Stage
Creatinine criterion
Urine output
Typical approach
Stage 1
×1.5–1.9 baseline or ↑ ≥0.3 mg/dL
<0.5 mL/kg/h × 6–12 h
Outpatient if pre-renal likely; remove offending agents; 48 h recheck
Stage 2
×2.0–2.9 baseline
<0.5 mL/kg/h × 12 h
Strong consideration for admission; close monitoring at minimum
Stage 3
×3.0 or Cr >4.0 mg/dL or initiation of KRT (kidney replacement therapy)
Test: Bedside bladder USS (post-void residual >300 mL) or renal USS (hydronephrosis bilateral). Relief of obstruction often restores function rapidly.
Action
Sick-day rules — medications to hold during AKI
NSAIDs — reduce renal blood flow via prostaglandin inhibition; worst in volume depletion ACEi / ARB — hold if volume depleted, K⁺ >5.5, or creatinine rising >25% within 2 weeks of initiation Metformin — hold if Cr >1.5 mg/dL in women, >1.7 in men, or any AKI (lactic acidosis risk) SGLT2 (sodium–glucose cotransporter-2) inhibitors — hold during any acute illness / hospitalisation (euglycaemic DKA risk) Contrast agents — schedule IV contrast procedures only when renal function stable Aminoglycosides — adjust dose per eGFR; avoid in AKI unless no alternative Beta-blockers — continue; do not stop abruptly Statins — continue
Admit If
Indications for hospital admission from the outpatient clinic
AKI Stage 2 or 3 · Oliguria or anuria · K⁺ >6.0 mEq/L or any ECG change · Volume overload with respiratory compromise · Creatinine rising >0.5 mg/dL in 24 h · Unknown aetiology requiring workup (GN, vasculitis) · Inability to take oral medications or maintain hydration at home · Social circumstances precluding safe outpatient monitoring
Outpatient AKI Monitoring Plan (Stage 1 Pre-renal — safe for outpatient)
If not improving or worsening at 48-h recheck → escalate to admission
FeNa / FeUrea Calculator — Pre-renal vs Intrinsic AKI
Creatinine:Urea nitrogen:
On diuretics? Add BUN values to calculate FeUrea (more reliable):
6
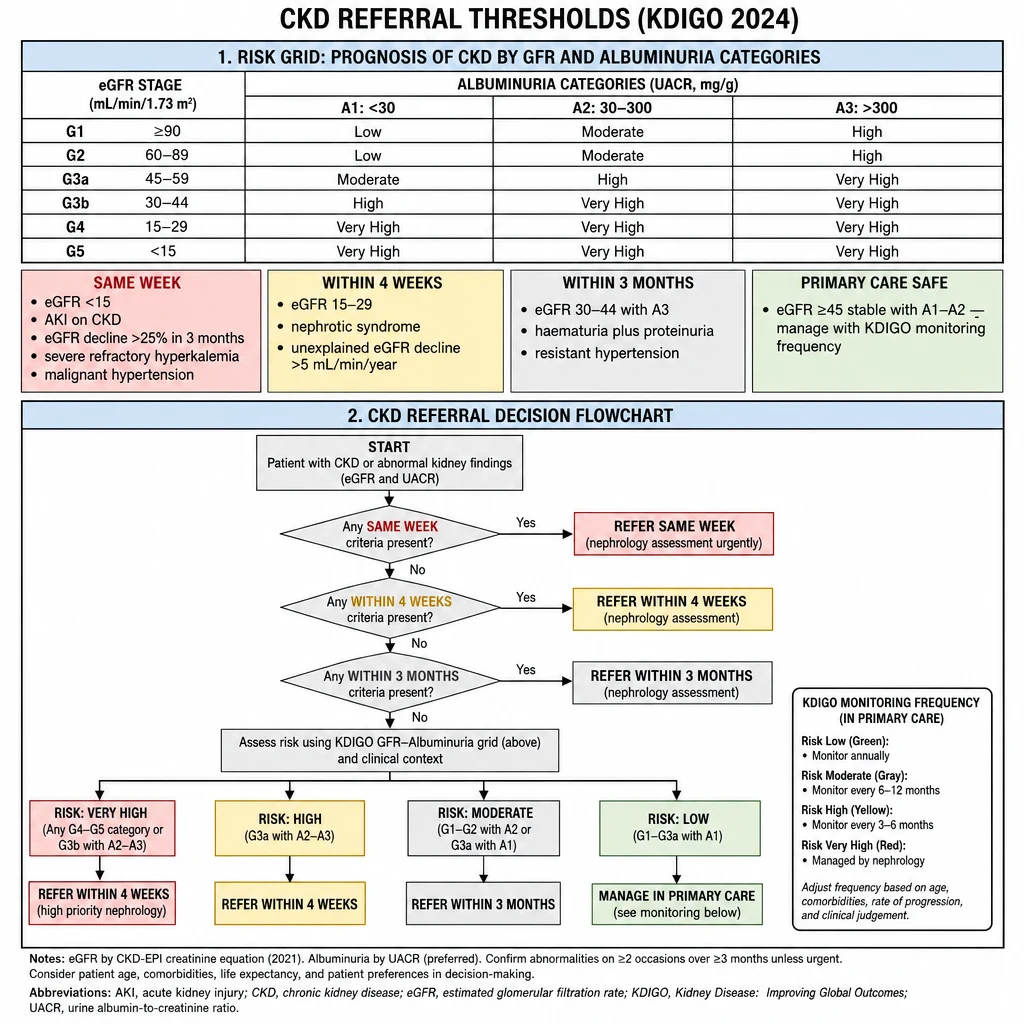
CKD Referral Thresholds
Based on KDIGO 2024 CKD guidelines. Referral is based on eGFR, albuminuria, rate of decline, and complications — not eGFR alone. Many patients with eGFR 45–60 can be safely managed in primary care with shared-care guidance.
CKD confirmed: eGFR <60 mL/min/1.73m² or urine ACR ≥30 mg/g on ≥2 occasions, ≥3 months apart
Confirm CKD staging using both eGFR (G1–G5) and albuminuria (A1–A3) — the G×A heatmap guides risk and referral urgency. A single creatinine is insufficient; trends over time matter most.
Urgent (<1 week)
Refer urgently — same week or emergency department
eGFR <15 mL/min/1.73m² (G5) — KRT planning required urgently
Suspected rapidly progressive GN: hematuria + proteinuria + creatinine rising over weeks (RPGN may progress to dialysis-dependence within weeks if untreated)
Hyperkalaemia >6.5 mEq/L not responding to emergency measures
Hypertensive emergency with new renal impairment
Pulmonary edema with new oliguria
Suspected hemolytic uraemic syndrome (microangiopathic hemolytic anemia + thrombocytopaenia + AKI)
Prompt (<1 month)
Refer within 4 weeks
eGFR <30 mL/min/1.73m² (G4) — KRT preparation, AVF (arteriovenous fistula) planning, anemia management, metabolic acidosis
eGFR decline >5 mL/min/1.73m²/year (rapid progressor) or >10 mL/min in 5 years
Persistent urine ACR >300 mg/g despite optimised ACEi/ARB + BP control
Recurrent AKI episodes (>3 per year)
Difficult-to-manage HTN with CKD (suspected renovascular or secondary cause)
Inherited kidney disease: PKD, Alport syndrome, FSGS (focal segmental glomerulosclerosis) in young patient
Unexplained proteinuria >1 g/g without diabetes or HTN
Routine (<3 months)
Refer within 3 months or co-manage with nephrology guidance
eGFR 30–44 (G3b) with any of: anemia Hgb (hemoglobin) <11, metabolic acidosis HCO₃ <22, CKD-MBD (↑PTH, ↑PO₄, ↓Ca), persistent hyperkalaemia
Diabetic nephropathy G3a+ with ACR >300 despite maximal dual RAS blockade
CKD with suspected glomerular disease (hematuria + proteinuria, abnormal sediment)
CKD requiring biopsy for diagnosis (proteinuria without clear cause)
Monitor
Safe to manage in primary care — monitor per KDIGO frequency
eGFR ≥45 (G1–G3a) + ACR <30 (A1) + controlled BP + controlled diabetes → annual nephrology review may be deferred
Review frequency by G×A risk category: Low (G1–G2, A1) = annual; Moderate (G3a, A1) = annual; High (G3a A2, G3b A1) = 2×/year; Very High = 3–4×/year
Monitor: BP, eGFR, ACR, electrolytes (K⁺, HCO₃), Hgb, Ca, PO₄, PTH (if eGFR <45)
Rule of thumb: Refer when you would question your next step
eGFR <30 → always refer (G4/G5)
ACR >300 persistent → always refer
Rapidly declining eGFR → always refer
Any doubt about aetiology → refer for biopsy consideration
AVF planning: Refer vascular surgery when eGFR <25 and HD (hemodialysis) is likely trajectory — earlier creation means better maturation
Transplant referral: eGFR <20 and declining — pre-emptive transplant is the best option
CKD-EPI 2021 eGFR Calculator
Creatinine units:
CKD anemia workflow
Start with a complete blood count (CBC), reticulocyte count, ferritin, and transferrin saturation (TSAT). Adult anemia is Hb <13 g/dL in men or <12 g/dL in women; pediatric thresholds are age-specific. Kidney disease does not exclude another cause.
If the initial tests do not explain anemia, tailor further testing: smear, haptoglobin/lactate dehydrogenase, C-reactive protein, B12/folate, liver tests, thyroid-stimulating hormone, parathyroid hormone, and monoclonal-protein studies. Assess blood loss and nutrition. Ferritin <45 ng/mL, or unexplained microcytosis without a ferritin result or known genetic cause, warrants evaluation for bleeding and appropriate referral (practice points 1.2.1–1.2.3, S19–20).
Population / decision
KDIGO 2026 guidance
Anemia + hemodialysis (HD): initiate iron
Ferritin ≤500 ng/mL and TSAT ≤30%. IV iron is suggested; use a proactive, monitored approach.
Anemia + non-dialysis CKD or peritoneal dialysis (PD): initiate iron
Ferritin <100 ng/mL and TSAT <40%, or ferritin ≥100 and <300 ng/mL and TSAT <25%.
Route outside HD
Choose oral or IV iron using severity, response, tolerance, preference, availability, and cost. Switch an optimal oral regimen to IV if ineffective after 1–3 months or poorly tolerated.
Withhold routine iron
Ferritin >700 ng/mL or TSAT ≥40%. An elevated ferritin alone does not diagnose iron overload.
Systemic infection
Consider temporarily suspending iron. Inflammation without infection needs clinical assessment rather than an automatic infection diagnosis.
Monitoring during iron treatment
Hb, ferritin, TSAT every 3 months in non-dialysis CKD/PD; every 1–3 months in HD, often monthly. Test sooner after blood loss, hospitalization, erythropoiesis-stimulating agent (ESA) escalation, or rapidly changing iron indices.
Decision
KDIGO 2026 guidance
Adult HD or PD: consider initiation
After reversible causes are addressed, consider ESA when Hb is ≤9–10 g/dL. Select the threshold within that range using symptoms, risks, and patient preferences.
Non-dialysis CKD, including transplant recipients
Individualize initiation using symptoms, potential benefit, transfusion avoidance, ESA risks, and preferences; Hb <10 alone is not an automatic start order.
Adult maintenance goal
Target Hb below 11.5 g/dL (115 g/L), individualized. A common working range is about 10 to <11.5 g/dL; this is not an anemia diagnostic range.
Dose changes
Use the lowest effective dose. Generally avoid adjustments more often than every 4 weeks. If Hb rises >1 g/dL in 2–4 weeks, reduce by 25–50%. Prefer reduction to holding while Hb does not exceed 11.5, as clinically appropriate.
Monitoring
Hb every 2–4 weeks after initiation or adjustment; at least every 3 months during maintenance, usually more often in HD.
Stroke, thrombosis, and cancer
Consider suspending ESA during hospitalization for acute stroke, vascular access thrombosis, or thromboembolism. Active or previous cancer calls for shared decision-making, especially when treatment aims at cure. Uncontrolled hypertension and product-specific contraindications require review.
Agent
Adult non-dialysis CKD examples
Adult HD/PD examples
Epoetin alfa / beta
About 50 U/kg once or twice weekly; adapt to regional product label.
50–100 U/kg three times weekly; confirm product and route.
Darbepoetin
0.45 µg/kg weekly, or 40–100 µg every 2–4 weeks, individualized.
0.45 µg/kg weekly or 0.75 µg/kg every 2 weeks.
Methoxy polyethylene glycol–epoetin beta (CERA)
0.6 µg/kg every 2 weeks; other monthly regimens are product-specific.
0.6 µg/kg every 2 weeks; conversion and monthly maintenance require product-label review.
Examples are from KDIGO 2026 Table 7 (S55), not interchangeable prescriptions. Do not infer injection frequency from a weekly total or switch products using an unvalidated ratio. Use the locally approved label, route, vial strengths, and facility protocol.
Investigate iron deficiency or iron-restricted erythropoiesis, inflammation/infection, bleeding, hemolysis, nutritional deficiency, hyperparathyroidism, inadequate dialysis, adherence, and marrow disease before escalating an erythropoiesis-stimulating agent (ESA). A sudden Hb decline with severe reticulocytopenia raises concern for pure red cell aplasia and requires specialist evaluation.
The ESA resistance index (ERI) is weekly epoetin dose ÷ weight ÷ Hb in g/dL. It is a longitudinal exposure/response measure, not a stand-alone diagnosis or instruction to maintain a dose. KDIGO 2026 Table 10 summarizes heterogeneous definitions; ERI 10 is not a universal KDIGO cutoff. Darbepoetin-to-epoetin conversions are approximate and dose-dependent; do not apply a fixed 200-IU/µg factor to CERA as a validated conversion.
For chronic anemia in CKD, base red-cell transfusion on symptoms and signs attributable to anemia and the individual balance of benefits and harms, rather than an arbitrary Hb threshold (practice point 4.4). Restrictive thresholds from other settings are context-specific and are not universal CKD orders.
Acute hemorrhage, unstable coronary disease, or urgent surgery may require rapid correction. Avoid transfusion when possible in transplant candidates to reduce allosensitization. Leukoreduction does not eliminate sensitization risk. When transfusion is appropriate, account for volume overload, potassium, iron burden, and reassess the response; stable patients are often managed one unit at a time under local protocols.
Source: KDIGO 2026 Anemia in CKD, recommendations 2.1–2.4 and 3.2.1–3.3.1; practice points 2.2–2.8 and 3.4.1.2–3.4.3.5. Reviewed November 6, 2026. Apply clinical judgment and the locally approved product label.
8
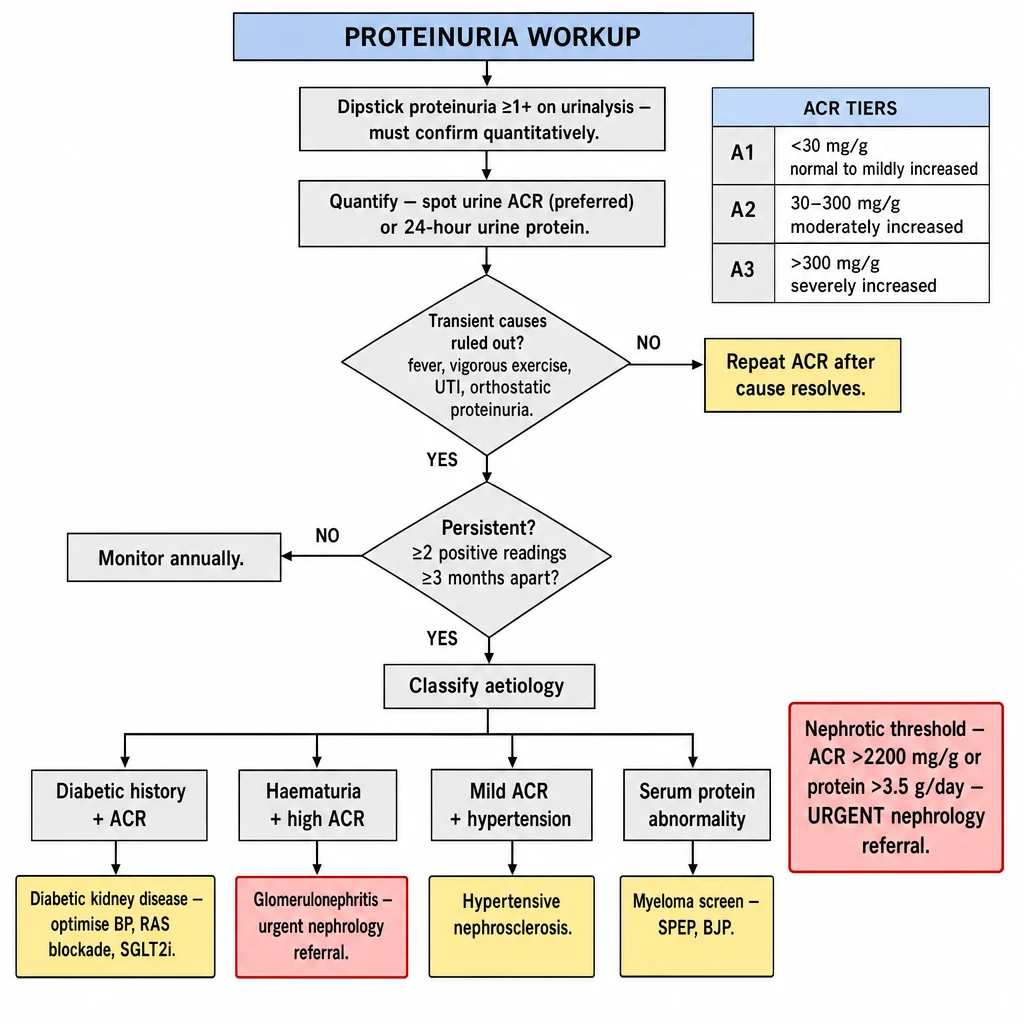
Proteinuria Workup
Proteinuria on dipstick must be confirmed quantitatively and be persistent (≥2 readings ≥3 months apart) to diagnose CKD. The degree and pattern guide the diagnostic pathway.
Macroalbuminuria — refer nephrology; high progression and cardiovascular disease (CVD) risk
>2,200 mg/g
Nephrotic range
Evaluate for nephrotic syndrome — urgent nephrology referral
Decision
Is the proteinuria transient or persistent?
Repeat ACR in 2–4 weeks. Instruct patient to avoid: vigorous exercise (within 24 h), fever, UTI, menstruation, prolonged upright posture. Orthostatic proteinuria: Common in adolescents and young adults. Protein present only in upright urine; absent in first morning void (supine overnight). Benign; confirm with split urine collection.
Transient or orthostatic
Reassure. Repeat ACR in 6–12 months. No treatment needed. If ACR normalises and remains normal — not CKD.
Persistent (≥2 occasions)
Classify aetiology and determine CKD stage with eGFR. Proceed with workup below.
Decision
What is the likely aetiology?
Diabetic nephropathy (DN)
Diabetes + ACR 30–300 (microalbuminuria) + NO hematuria + eGFR may be normal or ↓
Typically gradual onset; bilateral kidneys normal size or enlarged
Management: ACEi or ARB (first-line) · SGLT2i (canagliflozin, empagliflozin) · BP <130/80 · HbA1c (glycated hemoglobin) <7% · Finerenone if ACR >300 + eGFR 25–75
Refer if ACR >300 or eGFR declining despite optimised therapy
Non-diabetic proteinuria
Check: ANA, anti-dsDNA (lupus) · ANCA (vasculitis) · C3/C4 (complement-mediated) · Anti-PLA2R (MN) · SPEP/UPEP (myeloma if >40 y/o) · Hepatitis B/C serology · HIV (human immunodeficiency virus)
Active urine sediment (RBC casts, dysmorphic RBCs) → GN → urgent nephrology
Heavy proteinuria + normal urine sediment → membranous nephropathy or FSGS → refer
Nephrotic Syndrome
Nephrotic syndrome diagnosis — always refer to nephrology
Classic triad: Proteinuria >3.5 g/day + Serum albumin <3.0 g/dL + Pitting edema (± hyperlipidaemia, lipiduria). Causes in Filipino adults: Membranous nephropathy (most common adult-onset) · FSGS · Minimal change disease (often steroid-responsive) · Amyloidosis (if myeloma, chronic infection, or FMF) · Diabetic nephropathy (if heavy). Complications to manage while awaiting nephrology: Thromboembolism (PE risk when albumin <2.0 — consider anticoagulation) · Infection risk (encapsulated organisms — vaccinate) · Hyperlipidaemia (statin).
Baseline: eGFR, electrolytes, albumin, LFTs, CBC, BP
Diabetic: ACEi/ARB + SGLT2i + BP control → refer if ACR >300 or declining
Non-diabetic + hematuria + casts → GN → urgent nephrology
Nephrotic range → always refer → biopsy usually required
ACR 30–300 stable + diabetes/HTN controlled → manage in primary care
9
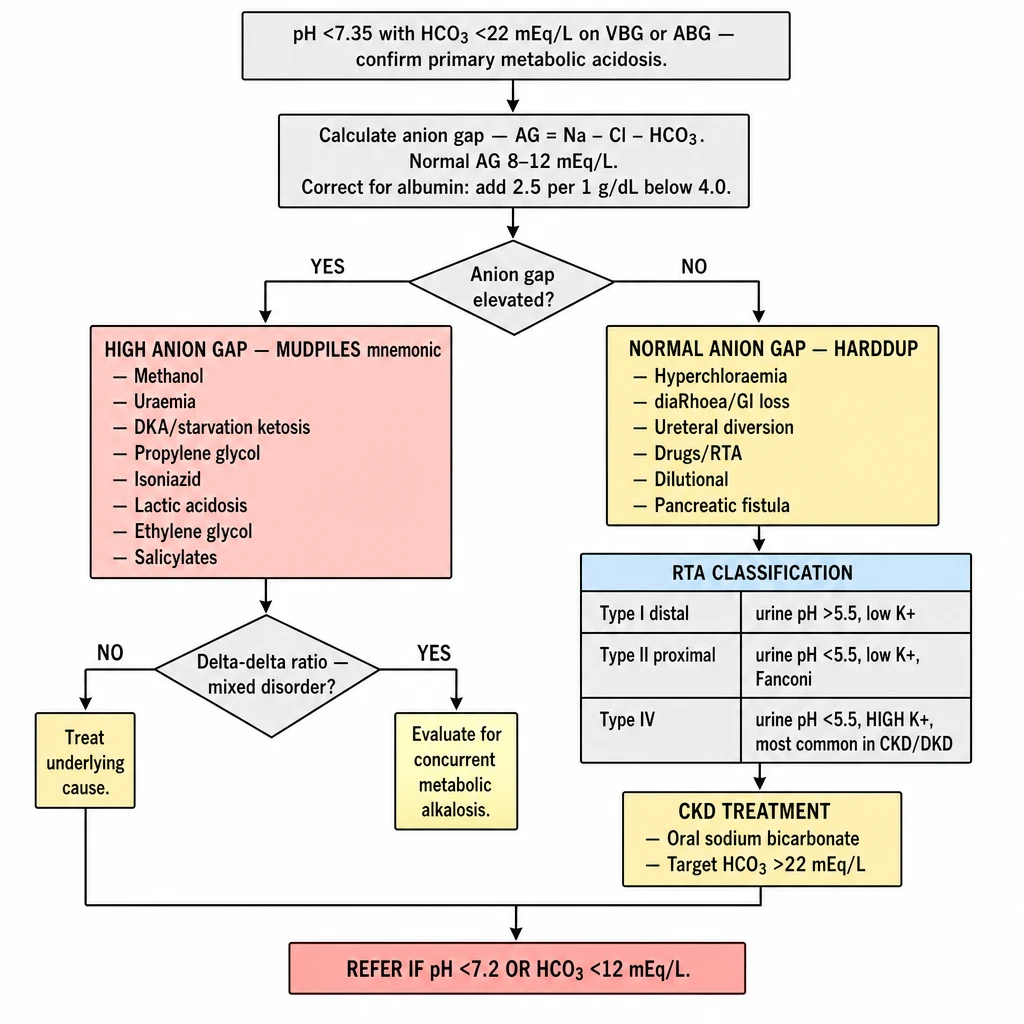
Metabolic Acidosis Correction
Step-wise approach: confirm the primary disorder, calculate the anion gap (with albumin correction), classify, then treat the cause. CKD metabolic acidosis (Type IV RTA and uraemic acidosis) are the most common outpatient presentations.
Algorithm 9 overview — Metabolic Acidosis. Confirm: pH <7.35, HCO₃ <22. Calculate AG (Na − Cl − HCO₃; correct for albumin). High AG (MUDPILES): uremia, DKA, lactic acidosis, toxins. Normal AG (HARDDUP): hyperchloraemic — RTA types I/II/IV, diarrhoea. CKD treatment: oral NaHCO₃, target HCO₃ >22. Refer if pH <7.2.
Trigger
ABG or venous blood gas showing pH <7.35 with HCO₃ <22 mEq/L
Step 1: Confirm primary disorder and assess compensation. Winter's formula (expected pCO₂ for pure metabolic acidosis):
Step 2: Calculate anion gap (AG) and correct for albumin
AG = Na⁺ − (Cl⁻ + HCO₃⁻) Normal: 8–12 mEq/L
Albumin-corrected AG = measured AG + [2.5 × (4.0 − albumin g/dL)]
↑ by 2.5 mEq/L for each 1 g/dL drop in albumin below 4.0
Delta-delta ratio (if high AG present):
δδ = (AG − 12) / (24 − HCO₃)
<0.4 → pure NAGMA (no AG component)
0.4–2 → pure HAGMA
>2 → HAGMA + concurrent metabolic alkalosis
Decision
Step 3: Classify by anion gap
High AG metabolic acidosis (HAGMA)
MUDPILES mnemonic:
Methanol poisoning
Uraemia (CKD G4–G5)
DKA / alcoholic / starvation ketoacidosis
Propylene glycol (IV medications)
Isoniazid / Iron toxicity
Lactic acidosis (Type A: hypoperfusion; Type B: metformin, liver disease)
Ethylene glycol (antifreeze)
Salicylate toxicity
Calculate osmolar gap if toxic alcohol suspected: OG = measured Osm − calculated Osm. OG >10 → toxic alcohol.
Normal AG (NAGMA / hyperchloraemic)
Calculate urine anion gap (UAG):
UAG = UNa + UK − UCl
Negative UAG (−): Appropriate NH₄⁺ excretion. Extra-renal cause: diarrhoea (most common in PH), ileostomy, fistula. → Treat with oral NaHCO₃ or K-citrate.
Sodium bicarbonate (NaHCO₃):
Starting dose: 0.5–1.0 mEq/kg/day divided into 2–3 doses with meals
Tablet: NaHCO₃ 650 mg = 7.7 mEq HCO₃ (available in PH pharmacies)
Powder: Baking soda (sodium bicarbonate) 1 level teaspoon = 48 mEq — practical and inexpensive for PH patients
Titrate every 4 weeks until HCO₃ reaches 22–26 mEq/L
Caution with sodium load: Each gram NaHCO₃ = 12 mEq Na⁺ — monitor BP and edema. If fluid overload is a concern, consider potassium citrate (if K⁺ is normal or low) as a sodium-free alternative.
Benefits beyond acidosis correction: Improved muscle protein retention · Reduced phosphate release from bone · Better response to erythropoietin (EPO) · Reduced hyperkalaemia (see Algorithm 2)
Refer
When to refer metabolic acidosis to nephrology or toxicology
Severe acidaemia: pH <7.20 or HCO₃ <10 → hospital (may need IV NaHCO₃ or haemodialysis) · Lactic acidosis type A (sepsis, shock) → ICU (intensive care unit) · Toxic alcohol ingestion (methanol, ethylene glycol) → emergency department + toxicology · Type I or II RTA with nephrocalcinosis/stones or Fanconi syndrome → nephrology · CKD acidosis not responding to oral NaHCO₃ at 1 mEq/kg/day → nephrology co-management
Quick Reference — Metabolic Acidosis Formulas
Anion gap: Na − (Cl + HCO₃) · Normal 8–12 mEq/L
Albumin correction: AG + 2.5 × (4 − Alb)
Winter's formula: pCO₂ = (1.5 × HCO₃) + 8 ± 2
Delta-delta: (AG−12) / (24−HCO₃)
Urine AG: UNa + UK − UCl · Negative = GI loss · Positive = RTA
NaHCO₃ 650 mg tab = 7.7 mEq HCO₃
Baking soda 1 tsp = ~48 mEq NaHCO₃ (practical for home use)
Type IV RTA = most common CKD acidosis; hyperkalemia + mild NAGMA in DKD
Electrolyte & Osmolality ToolkitToolkit sa Electrolyte at OsmolalityToolkit sa Electrolyte ug OsmolalityToolkit para king Electrolyte at Osmolality
Three clinician-facing calculators that complement the algorithms above: serum osmolality with osmolal gap (to flag toxic alcohols and other unmeasured osmoles), free water deficit for hypernatremia correction, and fractional excretion of urea (FEUrea) — the prerenal-vs-intrinsic discriminator of choice when the patient is on diuretics and FENa is unreliable.Tatlong calculator para sa mga clinician na dumadagdag sa mga algorithm sa itaas: serum osmolality na may osmolal gap (para matukoy ang toxic alcohols at iba pang hindi nasusukat na osmoles), free water deficit para sa pagtatama ng hypernatremia, at fractional excretion of urea (FEUrea) — ang piniling pamantayan ng prerenal-laban-intrinsic kapag ang pasyente ay gumagamit ng diuretics at hindi maaasahan ang FENa.Tulo ka calculator para sa mga clinician nga modugang sa mga algorithm sa ibabaw: serum osmolality nga adunay osmolal gap (aron mailhan ang toxic alcohols ug uban pang dili masukod nga osmoles), free water deficit para sa pagtul-id sa hypernatremia, ug fractional excretion of urea (FEUrea) — ang pinili nga timailhan sa prerenal-batok-intrinsic kon ang pasyente naggamit ug diuretics ug dili kasaligan ang FENa.Atlung calculator para king clinician a midagdag king algorithm a babo: serum osmolality a atin osmolal gap (para mikilala ya ing toxic alcohols at aliwa pang e masukat a osmoles), free water deficit para king pamanutul king hypernatremia, at fractional excretion of urea (FEUrea) — ing piling pamamaran ning prerenal-laban-intrinsic nung ing pasyente maki-diuretics ya at e mapagkatiwalaan ing FENa.
Serum Osmolality & Osmolal Gap
Glucose:Urea nitrogen:
From the lab (freezing-point depression). Needed for the osmolal gap.
Free Water Deficit — Hypernatremia
TBW fraction × weight. Lower in elderly / females.
FEUrea — Prerenal vs Intrinsic (reliable on diuretics)
Use FEUrea instead of FENa when the patient is on diuretics.
Kidney Disease: Improving Global Outcomes (KDIGO) CKD Work Group. (2024). KDIGO 2024 clinical practice guideline for the evaluation and management of chronic kidney disease. Kidney International, 105(4S), S117–S314. KDIGO CKD guideline
Kidney Disease: Improving Global Outcomes (KDIGO) Acute Kidney Injury Work Group. (2012). KDIGO clinical practice guideline for acute kidney injury. Kidney International Supplements, 2(1), 1–138. KDIGO AKI guideline
Whelton, P. K., Carey, R. M., Aronow, W. S., Casey, D. E., Collins, K. J., Dennison Himmelfarb, C., DePalma, S. M., Gidding, S., Jamerson, K. A., Jones, D. W., MacLaughlin, E. J., Muntner, P., Ovbiagele, B., Smith, S. C., Spencer, C. C., Stafford, R. S., Taler, S. J., Thomas, R. J., Williams, K. A., & ... Wright, J. T. (2018). 2017 ACC/AHA/AAPA/ABC/ACPM/AGS/apha/ASH/ASPC/NMA/PCNA guideline for the prevention, detection, evaluation, and management of high blood pressure in adults: executive summary: a report of the american college of cardiology/american heart association task force on clinical practice guidelines. Hypertension, 71(6), 1269–1324. https://doi.org/10.1161/HYP.0000000000000066
Williams, B., MacDonald, T. M., Morant, S., Webb, D. J., Sever, P., McInnes, G., Ford, I., Cruickshank, J. K., Caulfield, M. J., Salsbury, J., Mackenzie, I., Padmanabhan, S., Brown, M. J., & British Hypertension Society's PATHWAY Studies Group (2015). Spironolactone versus placebo, bisoprolol, and doxazosin to determine the optimal treatment for drug-resistant hypertension (PATHWAY-2): a randomised, double-blind, crossover trial. The Lancet, 386(10008), 2059–2068. https://doi.org/10.1016/S0140-6736(15)00257-3
Pfeffer, M. A., Burdmann, E. A., Chen, C.-Y., Cooper, M. E., de Zeeuw, D., Eckardt, K.-U., Feyzi, J. M., Ivanovich, P., Kewalramani, R., Levey, A. S., Lewis, E. F., McGill, J. B., McMurray, J. J. V., Parfrey, P., Parving, H.-H., Remuzzi, G., Singh, A. K., Solomon, S. D., & Toto, R. (2009). A trial of darbepoetin alfa in type 2 diabetes and chronic kidney disease. The New England Journal of Medicine, 361(21), 2019–2032. https://doi.org/10.1056/NEJMoa0907845
Inker, L. A., Eneanya, N. D., Coresh, J., Tighiouart, H., Wang, D., Sang, Y., Crews, D. C., Doria, A., Estrella, M. M., Froissart, M., Grams, M. E., Greene, T., Grubb, A., Gudnason, V., Gutiérrez, O. M., Kalil, R., Karger, A. B., Mauer, M., Navis, G., & ... Chronic Kidney Disease Epidemiology Collaboration (2021). New creatinine- and cystatin C-based equations to estimate GFR without race. The New England Journal of Medicine, 385(19), 1737–1749. https://doi.org/10.1056/NEJMoa2102953
Spasovski, G., Vanholder, R., Allolio, B., Annane, D., Ball, S., Bichet, D., Decaux, G., Fenske, W., Hoorn, E. J., Ichai, C., Joannidis, M., Soupart, A., Zietse, R., Haller, M., van der Veer, S., Van Biesen, W., Nagler, E., & Hyponatraemia Guideline Development Group (2014). Clinical practice guideline on diagnosis and treatment of hyponatraemia. European Journal of Endocrinology, 170(3), G1-47. https://doi.org/10.1530/EJE-13-1020
W Rivero, MD, FPCP, DPSN
Nephrologist · Internal Medicine · PhilippinesNephrologist · Internal Medicine · PilipinasNephrologist · Internal Medicine · PilipinasNephrologist · Internal Medicine · Pilipinas
Last reviewed: Huling sinuri: Katapusang gisusi: Huling sinuri:
Scan and saveI-scan at i-saveI-scan ug i-saveI-scan at i-save