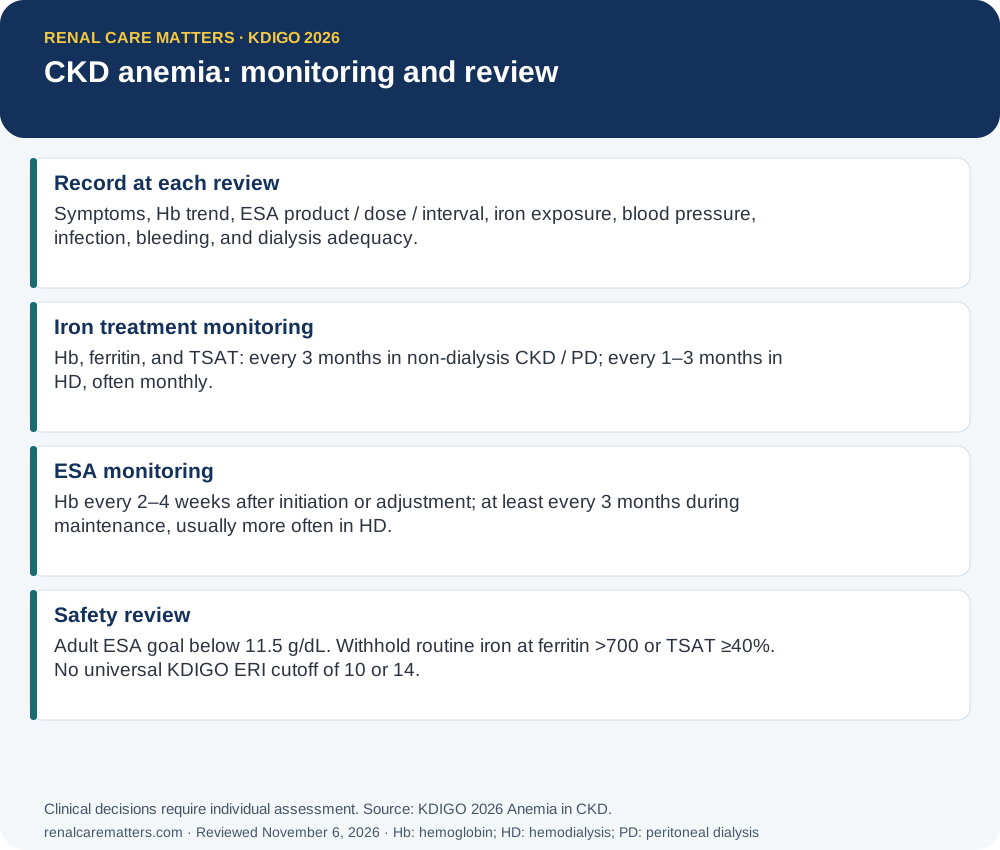
CKD anemia content reviewed November 6, 2026 against KDIGO 2026. See the population-specific KDIGO 2026 rules.
What Is Anemia — and Why Does It Matter?Ano ang Anemia — at Bakit Ito Mahalaga?Unsa ang Anemia — ug Nganong Importante Kini? Ano ing Anemia — at Bakit Ini Importante?

Anemia means your blood does not carry enough oxygen to meet your body's needs. Red blood cells contain hemoglobin — the protein that picks up oxygen in the lungs and delivers it to every organ. When hemoglobin falls too low, every organ suffers — especially the heart (which works harder) and the kidneys (which need oxygen to maintain filtration).Ang anemia ay nangangahulugang ang inyong dugo ay hindi nagdadala ng sapat na oxygen para matugunan ang pangangailangan ng katawan. Ang mga pulang selula ng dugo ay naglalaman ng hemoglobin — ang protina na kumukuha ng oxygen sa baga at naghahatid nito sa bawat organo. Kapag masyadong bumaba ang hemoglobin, nagdurusa ang bawat organo — lalo na ang puso (na nagtatrabaho nang mas malakas) at ang mga bato (na nangangailangan ng oxygen upang mapanatili ang pagsasala).Ang anemia nagpasabot nga ang inyong dugo dili magdala og igo nga oxygen aron matubag ang mga pangangailangan sa lawas. Ang mga pulang selula sa dugo adunay hemoglobin — ang protina nga mokuha og oxygen sa baga ug maghatod niini sa matag organo. Kon mubaba kaayo ang hemoglobin, mag-antos ang matag organo — ilabi na ang kasingkasing (nga nagbuhat og mas kusog) ug ang mga kidney (nga nanginahanglan og oxygen aron mapadayon ang pagsala). Ing anemia ya nangangahulugang ing inyu daya ya ali nagdadala ning sapat a oxygen para matugunan ing pangangailangan ning bangkî. Ing deng pulang selula ning daya ya naglalaman ning hemoglobin — ing protina a kumukuha ning oxygen king baga at naghahatid nini king bawat organo. Nung masyadong bumaba ing hemoglobin, nagdurusa ing bawat organo — lalo a ing pusu (a nagtatrabaho nang mas malakas) at ing deng batu (a nangangailangan ning oxygen upang mapanatili ing pagsasala).
In adults, anemia means hemoglobin (Hb) below 13 g/dL in men or 12 g/dL in women. Children need age-specific criteria. Diagnosis is separate from the treatment goal: adults taking an ESA should have an individualized Hb goal below 11.5 g/dL. Children require individualized specialist targets.
Sa adult, anemia ang hemoglobin (Hb) na mas mababa sa 13 g/dL sa lalaki o 12 g/dL sa babae. Sa bata, ayon sa edad ang pamantayan. Magkaiba ang diagnosis at layunin ng paggamot: sa adult na naka-ESA, indibidwal ang layunin at mas mababa sa 11.5 g/dL. Kailangan ng espesyalistang magtakda ng layunin para sa bata.
Sa hamtong, anemia ang hemoglobin (Hb) nga ubos sa 13 g/dL sa lalaki o 12 g/dL sa babaye. Sa bata, ang sukdanan nagdepende sa edad. Lahi ang diagnosis ug tumong sa pagtambal: sa hamtong nga nag-ESA, ipahaom ang tumong ug ipabilin nga ubos sa 11.5 g/dL. Ang espesyalista motakda sa tumong sa bata.
King adult, anemia ing hemoglobin (Hb) a mas mababa king 13 g/dL king lalaki o 12 g/dL king babae. King anak, agpang king edad ing pamantayan. Miyayaliwa ing diagnosis at layunin ning gamutan: king adult a maki-ESA, me-personalize ing layunin at mas mababa king 11.5 g/dL. Ing espesyalista ing magtakda ning layunin para king anak.

This illustration shows the four main reasons damaged kidneys lead to anemia: too little EPO (erythropoietin) hormone, iron locked away by hepcidin, red blood cells that wear out faster, and bone marrow that makes fewer cells.
CKD anemia is multifactorial — EPO deficiency, iron-restricted erythropoiesis, and shortened RBC (red blood cell) survival all contribute simultaneously. All three must be addressed.Ang anemia sa CKD ay may maraming dahilan — ang kakulangan ng EPO, ang iron-restricted erythropoiesis, at ang pinaikling buhay ng RBC ay sabay-sabay na nag-aambag. Ang lahat ng tatlo ay dapat tugunan.Ang anemia sa CKD adunay daghang hinungdan — ang kakulang sa EPO, ang iron-restricted erythropoiesis, ug ang gipamubo nga kinabuhi sa RBC nagambibit tanan sa dungan. Ang tanan nga tulo kinahanglan nga sulbaron. Ing anemia king CKD ya atin dacal a dahilan — ing kakulangan ning EPO, ing iron-restricted erythropoiesis, at ing pinaikling biye ning RBC ya sabay-sabay a nag-aambag. Ing amin ning tatlo ya dapat tugunan.
Symptoms of anemiaMga sintomas ng anemiaMga sintomas sa anemia Deng sintomas ning anemia
Persistent fatigue and weakness even with rest, shortness of breath on mild exertion, palpitations or rapid heartbeat, pale skin, pale inner eyelids (conjunctival pallor), dizziness or light-headedness on standing, difficulty concentrating, cold intolerance, and reduced exercise capacity.Patuloy na pagod at kahinaan kahit may pahinga, igsi ng hininga sa magaang na pagsisikap, palpitasyon o mabilis na tibok ng puso, maputlang balat, maputlang panloob na talukap ng mata (conjunctival pallor), pagkahilo o pag-alinlangan sa pagtayo, kahirapan sa konsentrasyon, hindi pagtitiis sa lamig, at nabawasang kakayahan sa ehersisyo.Padayon nga pagkaluya ug kahuyang bisan may pahinga, kahapdos sa paghinga sa magaan nga paningkamot, palpitasyon o paspas nga tibok sa kasingkasing, mapulaw nga panit, mapulaw nga sulod sa talukap sa mata (conjunctival pallor), pagkahilo o pag-alingawngaw sa pagtindog, kalisod sa konsentrasyon, dili pagpas-an sa kabugnaw, ug nabuwang nga kakayahan sa ehersisyo. Patuloy a pagod at kahinaan kahit atin pahinga, igsi ning hininga king magaang a pagsisikap, palpitasyon o mabilis a tibok ning pusu, maputlang balat, maputlang panloob a talukap ning mata (conjunctival pallor), pagkahilo o pag-alinlangan king pagtayo, kahirapan king konsentrasyon, ali pagtitiis king lamig, at nabawasang kakayahan king ehersisyo.
Why anemia is dangerous in CKDBakit mapanganib ang anemia sa CKDNganong delikado ang anemia sa CKD Bakit mapanganib ing anemia king CKD
The heart compensates for anemia by beating faster and pumping more blood — chronic compensation causes left ventricular hypertrophy and eventual heart failure. In dialysis patients, anemia is independently associated with increased cardiovascular mortality, hospitalizations, and reduced quality of life.Ang puso ay nagbabayad para sa anemia sa pamamagitan ng mas mabilis na pagtibok at pagpump ng mas maraming dugo — ang patuloy na pagbabayad ay nagdudulot ng left ventricular hypertrophy at kalaunan ay pagpalya ng puso. Sa mga pasyenteng nasa dialysis, ang anemia ay independyenteng nauugnay sa pagtaas ng cardiovascular mortality, mga hospitalisasyon, at nabawasang kalidad ng buhay.Ang kasingkasing nagbayad alang sa anemia pinaagi sa mas paspas nga pagtibok ug pagpump sa mas daghang dugo — ang kronikong pagbayad nagdala sa left ventricular hypertrophy ug sa katapusan ay pagpaluya sa kasingkasing. Sa mga pasyente nga nag-dialysis, ang anemia adunay independyenteng kalabotan sa dugang cardiovascular mortality, mga hospitalisasyon, ug nabuwang nga kalidad sa kinabuhi. Ing pusu ya nagbabayad para king anemia king pamamagitan ning mas mabilis a pagtibok at pagpump ning mas dacal a daya — ing patuloy a pagbabayad ya nagdudulot ning left ventricular hypertrophy at kalaunan ya pagpalya ning pusu. King deng pasyenteng nasa dialysis, ing anemia ya independyenteng nauugnay king pagtaas ning cardiovascular mortality, deng hospitalisasyon, at nabawasang kalidad ning biye.
Common Causes of AnemiaMga Karaniwang Sanhi ng AnemiaMga Kasagarang Hinungdan sa Anemia Deng Karaniwang Sanhi ning Anemia

This infographic outlines the common causes of anemia, including iron deficiency, low EPO from kidney disease, vitamin B12 or folate deficiency, anemia of chronic disease, thalassemia, and certain medications.
Iron deficiencyKakulangan ng ironKakulang sa iron Kakulangan ning iron
Most common cause globally. Blood loss (menstruation, GI bleeding), poor dietary intake, or poor absorption (gastritis, celiac).Pinaka-karaniwang sanhi sa buong mundo. Pagkawala ng dugo (regla, GI bleeding), mahinang pagkain, o mahinang pagsipsip (gastritis, celiac).Labing kasagarang hinungdan sa tibuok kalibutan. Pagkawala sa dugo (regla, GI bleeding), gamay nga pagkaon, o gamay nga pagsuyop (gastritis, celiac). Pinaka-karaniwang sanhi king buong mundo. Pagkaala ning daya (regla, GI bleeding), mahinang pamangan, o mahinang pagsipsip (gastritis, celiac).
CKD / EPO deficiencyCKD / Kakulangan ng EPOCKD / Kakulang sa EPO CKD / Kakulangan ning EPO
Failing kidneys produce insufficient erythropoietin — the hormone that signals bone marrow to make red blood cells.Ang mga bagsak na bato ay gumagawa ng kulang na erythropoietin — ang hormon na nagbibigay-senyal sa bone marrow na gumawa ng mga pulang selula ng dugo.Ang mga napakyas nga kidney nagpatunghag kulang nga erythropoietin — ang hormon nga nag-signal sa bone marrow nga maghimo og mga pulang selula sa dugo. Ing deng bagsak a batu ya gumagawa ning kulang a erythropoietin — ing hormon a nagbibigay-senyal king bone marrow a gumawa ning deng pulang selula ning daya.
B12 / Folate deficiencyKakulangan ng B12 / FolateKakulang sa B12 / Folate Kakulangan ning B12 / Folate
Required for DNA synthesis in red cell precursors. Deficiency causes large, immature cells (megaloblastic anemia).Kinakailangan para sa DNA synthesis sa mga precursor ng pulang selula. Ang kakulangan ay nagdudulot ng malalaki, hindi pa ganap na mga selula (megaloblastic anemia).Gikinahanglan alang sa DNA synthesis sa mga precursor sa pulang selula. Ang kakulang nagdala sa dagko, hilaw pa nga mga selula (megaloblastic anemia). Kinakailangan para king DNA synthesis king deng precursor ning pulang selula. Ing kakulangan ya nagdudulot ning malalaki, ali pa ganap a deng selula (megaloblastic anemia).
Anemia of chronic diseaseAnemia ng kronikong sakitAnemia sa kroniko nga sakit Anemia ning kronikong sakit
Inflammation from chronic illness (infection, autoimmune, cancer) sequesters iron and suppresses erythropoiesis via hepcidin.Ang pamamaga mula sa kronikong sakit (impeksyon, autoimmune, kanser) ay nagtatago ng iron at pumipigil sa erythropoiesis sa pamamagitan ng hepcidin.Ang pamamaga gikan sa kroniko nga sakit (impeksyon, autoimmune, kanser) nagtago sa iron ug nagpugong sa erythropoiesis pinaagi sa hepcidin. Ing pamamaga mula king kronikong sakit (impeksyon, autoimmune, kanser) ya nagtatago ning iron at pumipigil king erythropoiesis king pamamagitan ning hepcidin.
ThalassemiaThalassemiaThalassemia Thalassemia
Genetic disorder causing defective hemoglobin production. Common in Southeast Asia including the Philippines. Causes microcytic, hypochromic anemia resistant to iron therapy.Genetic disorder na nagdudulot ng depektibong produksyon ng hemoglobin. Karaniwan sa Timog-silangang Asya kasama ang Pilipinas. Nagdudulot ng microcytic, hypochromic anemia na lumalaban sa iron therapy.Genetic disorder nga nagdala sa depektibong produksyon sa hemoglobin. Kasagarang makita sa Timog-sidlakang Asya lakip ang Pilipinas. Nagdala sa microcytic, hypochromic anemia nga nagbatok sa iron therapy. Genetic disorder a nagdudulot ning depektibong produksyon ning hemoglobin. Karaniwan king Timog-silangang Asya kasama ing Pilipinas. Nagdudulot ning microcytic, hypochromic anemia a lumalaban king iron therapy.
Medication-relatedKaugnay sa gamotMay kalabotan sa tambal Kaugnay king gamut
ACE inhibitors, ARBs (angiotensin receptor blockers), immunosuppressants, and certain antibiotics can suppress red cell production or cause hemolysis.Ang ACE inhibitors, ARBs, immunosuppressants, at ilang antibiotics ay maaaring pigilan ang produksyon ng pulang selula o magdulot ng hemolysis.Ang ACE inhibitors, ARBs, immunosuppressants, ug pipila ka antibiotics mahimong pugngan ang produksyon sa pulang selula o makapahimong hemolysis. Ing ACE inhibitors, ARBs, immunosuppressants, at ilang antibiotics ya maaaring pigilan ing produksyon ning pulang selula o magdulot ning hemolysis.
Most CKD anemia is multifactorialAng karamihang anemia sa CKD ay may maraming dahilanAng kadaghanan sa anemia sa CKD adunay daghang hinungdan Ing karamihang anemia king CKD ya atin dacal a dahilan
In a CKD or dialysis patient, anemia is rarely from a single cause. The most common combination is EPO deficiency + iron deficiency + chronic inflammation — all three must be addressed simultaneously. Treating EPO deficiency alone without ensuring iron adequacy is a common cause of ESA (erythropoiesis-stimulating agent) therapy failure.Sa isang pasyenteng may CKD o nasa dialysis, ang anemia ay bihirang manggaling sa isang dahilan lamang. Ang pinakakaraniwang kombinasyon ay kakulangan ng EPO + kakulangan ng iron + kronikong pamamaga — ang lahat ng tatlo ay dapat tugunan nang sabay-sabay. Ang paggamot lamang sa kakulangan ng EPO nang hindi tinitiyak ang sapat na iron ay isang karaniwang sanhi ng pagkabigo ng ESA therapy.Sa usa ka pasyente nga may CKD o nag-dialysis, ang anemia panagsa ra gikan sa usa ka hinungdan lamang. Ang labing kasagarang kombinasyon mao ang kakulang sa EPO + kakulang sa iron + kroniko nga pamamaga — ang tanan nga tulo kinahanglan nga sulbaron sa dungan. Ang pagtambal lamang sa kakulang sa EPO nga wala masiguro ang sapat nga iron usa ka kasagarang hinungdan sa pagkapakyas sa ESA therapy. King metung a pasyenteng atin CKD o nasa dialysis, ing anemia ya bihirang manggaling king metung a dahilan lamang. Ing pinakakaraniwang kombinasyon ya kakulangan ning EPO + kakulangan ning iron + kronikong pamamaga — ing amin ning tatlo ya dapat tugunan nang sabay-sabay. Ing paggamut lamang king kakulangan ning EPO nang ali tinitiyak ing sapat a iron ya metung a karaniwang sanhi ning pagkabigo ning ESA therapy.
Why CKD Causes Anemia — The MechanismBakit Nagdudulot ng Anemia ang CKD — Ang MekanismoNganong Nagdala og Anemia ang CKD — Ang Mekanismo Bakit Nagdudulot ning Anemia ing CKD — Ing Mekanismo
Erythropoietin (EPO) deficiency — the primary driverKakulangan ng Erythropoietin (EPO) — ang pangunahing dahilanKakulang sa Erythropoietin (EPO) — ang panguna nga hinungdan Kakulangan ning Erythropoietin (EPO) — ing pangunahing dahilan
The peritubular cells of the kidney sense oxygen tension and produce erythropoietin in response to hypoxia. As kidney tissue is lost in CKD, EPO production falls proportionally. Without EPO, the bone marrow receives no signal to produce new red blood cells — existing cells age and die without replacement, causing progressive anemia.Ang mga peritubular cell ng bato ay nakakakita ng oxygen tension at gumagawa ng erythropoietin bilang tugon sa hypoxia. Habang nawawala ang tissue ng bato sa CKD, ang produksyon ng EPO ay bumababa nang proporsyonal. Nang wala ang EPO, ang bone marrow ay walang natatanggap na senyal para gumawa ng bagong mga pulang selula ng dugo — ang mga kasalukuyang selula ay tumatanda at namamatay nang walang kapalit, na nagdudulot ng progresibong anemia.Ang mga peritubular cell sa kidney nakabati sa oxygen tension ug nagpatunghag erythropoietin isip tubag sa hypoxia. Samtang mawala ang tissue sa kidney sa CKD, ang produksyon sa EPO nag-ubos sa proporsyon. Kung wala ang EPO, ang bone marrow walay madawat nga signal aron maghimo og bag-ong mga pulang selula sa dugo — ang mga naanaa nga selula nag-edad ug namatay nga walay kapuli, nagdala sa progresibong anemia. Ing deng peritubular cell ning batu ya nakakakita ning oxygen tension at gumagawa ning erythropoietin bilang tugon king hypoxia. Habang nawawala ing tissue ning batu king CKD, ing produksyon ning EPO ya bumababa nang proporsyonal. Nang ala ing EPO, ing bone marrow ya alang natatanggap a senyal para gumawa ning bagong deng pulang selula ning daya — ing deng kasalukuyang selula ya tumatanda at namamatay nang alang kapalit, a nagdudulot ning progresibong anemia.
Iron deficiency — absolute and functionalKakulangan ng iron — ganap at functionalKakulang sa iron — absoluto ug functional Kakulangan ning iron — ganap at functional
CKD patients lose iron through the dialysis circuit (blood remaining in tubing), frequent blood draws, and GI bleeding from uremic platelet dysfunction. Additionally, inflammation raises hepcidin — a hormone that blocks iron release from stores even when ferritin appears adequate. This pattern is called iron-restricted erythropoiesis (not enough iron reaching the marrow despite apparently adequate stores). In hemodialysis it often responds better to IV iron; in non-dialysis CKD, oral or IV iron can both be reasonable and the choice is individualized. Note that a rise in hemoglobin after IV iron does not by itself prove iron deficiency.Ang mga pasyenteng may CKD ay nawawalan ng iron sa pamamagitan ng dialysis circuit (dugo na nananatili sa tubing), madalas na pagkuha ng dugo, at GI bleeding mula sa uremic platelet dysfunction. Bukod dito, ang pamamaga ay nagpapataas ng hepcidin — isang hormon na humahadlang sa pagpapalabas ng iron mula sa mga imbakan kahit na tila sapat ang ferritin. Ang pattern na ito ay tinatawag na iron-restricted erythropoiesis (kulang ang iron na umaabot sa marrow kahit tila sapat ang imbak). Sa hemodialysis, madalas itong mas tumutugon sa IV iron; sa non-dialysis CKD, maaaring parehong makatwiran ang oral o IV iron at isinasapersonal ang pagpili. Tandaan: ang pagtaas ng hemoglobin pagkatapos ng IV iron ay hindi nagpapatunay mag-isa ng kakulangan sa iron.Ang mga pasyente nga may CKD nawad-an og iron pinaagi sa dialysis circuit (dugo nga nagpabilin sa tubing), kanunay nga pagkuha sa dugo, ug GI bleeding gikan sa uremic platelet dysfunction. Dugang pa, ang pamamaga nagpataas sa hepcidin — usa ka hormon nga nagpugong sa pagpagawas sa iron gikan sa mga imbakan bisan kung tila sapat ang ferritin. Kini nga pattern gitawag nga iron-restricted erythropoiesis (kulang ang iron nga moabot sa marrow bisan pa og tila igo ang stores). Sa hemodialysis, kasagaran mas motubag kini sa IV iron; sa non-dialysis CKD, mahimong pareho nga makatarunganon ang oral o IV iron ug ang pagpili gipahiangay sa tawo. Timan-i: ang pagsaka sa hemoglobin human sa IV iron dili magpamatuod nga mag-inusara sa kakulang sa iron. Ing deng pasyenteng atin CKD ya nawawalan ning iron king pamamagitan ning dialysis circuit (daya a nananatili king tubing), madalas a pagkuha ning daya, at GI bleeding mula king uremic platelet dysfunction. Bukod dini, ing pamamaga ya nagpapataas ning hepcidin — metung a hormon a humahadlang king pagpapalabas ning iron mula king deng imbakan kahit a tila sapat ing ferritin. Ing pattern a ini ya ausan dang iron-restricted erythropoiesis (kulang ing iron a datang king marrow kahit tila sapat ing imbak). King hemodialysis, madalas ini mas tumutugon king IV iron; king non-dialysis CKD, malyaring parehong makatwiran ing oral o IV iron at me-personalize ing pamamili. Tandaan: ing pagtaas ning hemoglobin kaibat ning IV iron ya ali nagpapatunay mag-isa ning kakulangan king iron.
Shortened red blood cell survivalPinaikling buhay ng pulang selula ng dugoGipamubo nga kinabuhi sa pulang selula sa dugo Pinaikling biye ning pulang selula ning daya
Uremic toxins damage red blood cell membranes, shortening their lifespan from the normal 120 days to as little as 60–90 days. Even with adequate EPO and iron, the bone marrow cannot produce cells fast enough to replace those being destroyed — worsening the anemia.Ang mga uremic toxin ay nagpapasama ng mga lamad ng pulang selula ng dugo, pinaikli ang kanilang buhay mula sa normal na 120 araw hanggang 60–90 araw lamang. Kahit may sapat na EPO at iron, ang bone marrow ay hindi makapaggawa ng mga selula nang mabilis upang mapalitan ang mga nasisira — nagpapalubha ng anemia.Ang mga uremic toxin nagdaot sa mga lamad sa pulang selula sa dugo, gipamubo ang ilang kinabuhi gikan sa normal nga 120 ka adlaw ngadto sa 60–90 ka adlaw lamang. Bisan may igo nga EPO ug iron, ang bone marrow dili makahimo og mga selula nga paspas aron mapuli ang mga ginadaot — nagpagrabe sa anemia. Ing deng uremic toxin ya nagpapasama ning deng lamad ning pulang selula ning daya, pinaikli ing kanilang biye mula king normal a 120 aldo anggang 60–90 aldo lamang. Kahit atin sapat a EPO at iron, ing bone marrow ya ali makapaggawa ning deng selula nang mabilis upang mapalitan ing deng nasisira — nagpapalubha ning anemia.
Secondary hyperparathyroidism — bone marrow fibrosisSecondary hyperparathyroidism — fibrosis ng bone marrowSecondary hyperparathyroidism — fibrosis sa bone marrow Secondary hyperparathyroidism — fibrosis ning bone marrow
Severely elevated PTH (parathyroid hormone) causes marrow fibrosis (osteitis fibrosa cystica) — replacing the normal marrow where red cells are made with fibrous tissue. This form of anemia responds poorly to EPO and iron — it requires control of PTH through active vitamin D, phosphate binders, and sometimes parathyroidectomy.Ang matinding pagtaas ng PTH ay nagdudulot ng marrow fibrosis (osteitis fibrosa cystica) — pinapalitan ang normal na marrow kung saan ginagawa ang mga pulang selula ng fibrous tissue. Ang anyang ito ay mahinang tumutugon sa EPO at iron — nangangailangan ito ng kontrol sa PTH sa pamamagitan ng active vitamin D, phosphate binders, at minsan parathyroidectomy.Ang grabeng pagtaas sa PTH nagdala sa marrow fibrosis (osteitis fibrosa cystica) — nagpuli sa normal nga marrow diin gihimo ang mga pulang selula pinaagi sa fibrous tissue. Kining matang sa anemia mahinay motubag sa EPO ug iron — nanginahanglan kini og kontrol sa PTH pinaagi sa active vitamin D, phosphate binders, ug usahay parathyroidectomy. Ing matinding pagtaas ning PTH ya nagdudulot ning marrow fibrosis (osteitis fibrosa cystica) — pinapalitan ing normal a marrow nung saan ginagawa ing deng pulang selula ning fibrous tissue. Ing anyang ini ya mahinang tumutugon king EPO at iron — nangangailangan ini ning kontrol king PTH king pamamagitan ning active vitamin D, phosphate binders, at misan parathyroidectomy.
Diagnosing and Classifying AnemiaPag-diagnose at Pag-uuri ng AnemiaPag-diagnose ug Pag-klase sa Anemia Pag-diagnose at Pag-uuri ning Anemia

This infographic explains how anemia in kidney disease is diagnosed and classified, using red cell size (MCV) categories and iron blood tests such as ferritin and transferrin saturation (TSAT).
Two KDIGO 2026 terms worth knowingDalawang termino ng KDIGO 2026 na dapat malamanDuha ka termino sa KDIGO 2026 nga angay mahibaloanAdwang termino ning KDIGO 2026 a dapat balu
Systemic iron deficiency means both circulating iron AND stored iron are low. Iron-restricted erythropoiesis means there is not enough circulating iron reaching the marrow despite apparently adequate stores — driven by inflammation and hepcidin, and by ESA-driven iron use. Ferritin and TSAT are the two markers used to tell these apart. They are imperfect (ferritin also rises with inflammation) but remain the principal trial-tested measures. Importantly, a rise in hemoglobin after IV iron does not by itself prove that iron deficiency was the problem.Ang systemic iron deficiency ay nangangahulugang mababa ang parehong umiikot (circulating) na iron AT nakaimbak na iron. Ang iron-restricted erythropoiesis ay nangangahulugang kulang ang umiikot na iron na umaabot sa marrow kahit tila sapat ang imbak — dulot ng pamamaga at hepcidin, at ng paggamit ng iron dahil sa ESA. Ang ferritin at TSAT ang dalawang marker na ginagamit upang pag-ibahin ang mga ito. Hindi sila perpekto (tumataas din ang ferritin sa pamamaga) ngunit nananatiling pangunahing sinubok-sa-pananaliksik na sukatan. Mahalaga: ang pagtaas ng hemoglobin pagkatapos ng IV iron ay hindi nagpapatunay mag-isa na kakulangan sa iron ang problema.Ang systemic iron deficiency nagpasabot nga ubos ang circulating iron UG stored iron. Ang iron-restricted erythropoiesis nagpasabot nga kulang ang circulating iron nga moabot sa marrow bisan tuod og tila igo ang stores — tungod sa pamamaga ug hepcidin, ug sa paggamit sa iron tungod sa ESA. Ang ferritin ug TSAT ang duha ka marker nga gigamit aron mailhan kini. Dili sila hingpit (ang ferritin mosaka usab sa pamamaga) apan nagpabilin nga panguna nga na-trial nga sukdanan. Importante: ang pagsaka sa hemoglobin human sa IV iron dili magpamatuod nga mag-inusara nga kakulang sa iron ang problema. Ing systemic iron deficiency ya buri nang sabian mababa ing parehong circulating a iron AT nakaimbak a iron. Ing iron-restricted erythropoiesis ya buri nang sabian kulang ing circulating a iron a datang king marrow kahit tila sapat ing imbak — dulut ning pamamaga at hepcidin, at ning pamangamit ning iron uli ning ESA. Ing ferritin at TSAT ing adwang marker a gagamitan para miyayaliwa la deti. Ali la perpektu (tutas mu naman ing ferritin king pamamaga) dapot manatili lang pangunang me-trial a sukatan. Importante: ing pagtaas ning hemoglobin kaibat ning IV iron ya ali nagpapatunay mag-isa a kakulangan king iron ing problema.
| TestPagsusuriPagsusiha Pagsusuri | What it identifiesAno ang natutukoy nitoUnsa ang natino niini Ano ing natutukoy nini | Key values to noteMahahalagang halaga na dapat tandaanMga importanteng kantidad nga hinumdoman Mahahalagang halaga a dapat tandaan |
|---|---|---|
| Hemoglobin (Hgb)Hemoglobin (Hgb)Hemoglobin (Hgb) Hemoglobin (Hgb) | Severity of anemiaKalubhaan ng anemiaGrabe nga anemia Kalubhaan ning anemia | Anemia: <130 g/L (men), <120 g/L (women). On an ESA, the goal is below 115 g/L, individualized. <80 = severe anemia requiring urgent evaluation.Anemia: <130 g/L (lalaki), <120 g/L (babae). Kung gumagamit ng ESA, ang layunin ay mas mababa sa 115 g/L, indibidwal. <80 = malubhang anemia na nangangailangan ng agarang pagsusuri.Anemia: <130 g/L (lalaki), <120 g/L (babaye). Kon naggamit og ESA, ang tumong ubos sa 115 g/L, ipahaom sa pasyente. <80 = grabeng anemia nga nanginahanglan og dinalian nga pagsusiha. Anemia: <130 g/L (lalaki), <120 g/L (babai). Nung gagamit ESA, ing layunin mas mababa king 115 g/L, me-personalize. <80 = malubhang anemia a nangangailangan ning agarang pagsusuri. |
| MCV (Mean Cell Volume)MCV (Mean Cell Volume)MCV (Mean Cell Volume) MCV (Mean Cell Volume) | Type of anemia by cell sizeUri ng anemia ayon sa laki ng selulaMatang sa anemia sumala sa gidak-on sa selula Uri ning anemia ayon king laki ning selula | <80 fL = microcytic (iron deficiency, thalassemia); >100 fL = macrocytic (B12/folate deficiency); 80–100 = normocytic (CKD, chronic disease, mixed)<80 fL = microcytic (kakulangan ng iron, thalassemia); >100 fL = macrocytic (kakulangan ng B12/folate); 80–100 = normocytic (CKD, kronikong sakit, halo-halo)<80 fL = microcytic (kakulang sa iron, thalassemia); >100 fL = macrocytic (kakulang sa B12/folate); 80–100 = normocytic (CKD, kroniko nga sakit, halo-halo) <80 fL = microcytic (kakulangan ning iron, thalassemia); >100 fL = macrocytic (kakulangan ning B12/folate); 80–100 = normocytic (CKD, kronikong sakit, halo-halo) |
| Serum ferritinSerum ferritinSerum ferritin Serum ferritin | Iron storesImbakan ng ironImbakan sa iron Imbakan ning iron | Read together with TSAT; inflammation raises ferritin. KDIGO 2026 iron-start limits: hemodialysis ≤500 ng/mL; non-dialysis CKD or PD <100, or 100 to <300 when TSAT is low. Routine iron is withheld above 700.Basahin kasama ang TSAT; tumataas ang ferritin sa pamamaga. Mga limitasyon ng KDIGO 2026 sa pagsisimula ng iron: hemodialysis ≤500 ng/mL; CKD na hindi naka-dialysis o PD <100, o 100 hanggang <300 kung mababa ang TSAT. Ipinagpapaliban ang regular na iron kapag lampas 700.Basaha uban sa TSAT; mosaka ang ferritin tungod sa pamamaga. Mga limitasyon sa KDIGO 2026 sa pagsugod sa iron: hemodialysis ≤500 ng/mL; CKD nga dili nag-dialysis o PD <100, o 100 hangtod <300 kon ubos ang TSAT. Dili ihatag ang regular nga iron kon molapas sa 700. Basan kayabe ing TSAT; tataas ing ferritin uli ning pamamaga. Deng limitasyon ning KDIGO 2026 king pamagumpisa ning iron: hemodialysis ≤500 ng/mL; CKD a ali naka-dialysis o PD <100, o 100 anggang <300 nung mababa ing TSAT. Ipagpaliban ing regular a iron nung lampas 700. |
| TSAT (Transferrin Saturation)TSAT (Transferrin Saturation)TSAT (Transferrin Saturation) TSAT (Transferrin Saturation) | Functional iron availability for erythropoiesisFunctional na availability ng iron para sa erythropoiesisFunctional nga availability sa iron alang sa erythropoiesis Functional a availability ning iron para king erythropoiesis | Read together with ferritin. A low TSAT with normal or high ferritin suggests iron-restricted erythropoiesis. KDIGO 2026 iron-start limits: hemodialysis ≤30%; non-dialysis CKD or PD <40% (ferritin <100) or <25% (ferritin 100 to <300). Routine iron is withheld at 40% or higher.Basahin kasama ang ferritin. Ang mababang TSAT na may normal o mataas na ferritin ay nagpapahiwatig ng iron-restricted erythropoiesis. Mga limitasyon ng KDIGO 2026 sa pagsisimula ng iron: hemodialysis ≤30%; CKD na hindi naka-dialysis o PD <40% (ferritin <100) o <25% (ferritin 100 hanggang <300). Ipinagpapaliban ang regular na iron sa 40% pataas.Basaha uban sa ferritin. Ang ubos nga TSAT nga may normal o taas nga ferritin nagpakita sa iron-restricted erythropoiesis. Mga limitasyon sa KDIGO 2026 sa pagsugod sa iron: hemodialysis ≤30%; CKD nga dili nag-dialysis o PD <40% (ferritin <100) o <25% (ferritin 100 hangtod <300). Dili ihatag ang regular nga iron kon 40% o labaw. Basan kayabe ing ferritin. Ing mababang TSAT a atin normal o matas a ferritin ya pakilala ning iron-restricted erythropoiesis. Deng limitasyon ning KDIGO 2026 king pamagumpisa ning iron: hemodialysis ≤30%; CKD a ali naka-dialysis o PD <40% (ferritin <100) o <25% (ferritin 100 anggang <300). Ipagpaliban ing regular a iron nung 40% o mas matas. |
| Reticulocyte count + CHrReticulocyte count + CHrReticulocyte count + CHr Reticulocyte count + CHr | Bone marrow response; iron adequacy for erythropoiesisTugon ng bone marrow; kasapatan ng iron para sa erythropoiesisTubag sa bone marrow; kasiguroan sa iron alang sa erythropoiesis Tugon ning bone marrow; kasapatan ning iron para king erythropoiesis | Low reticulocytes = insufficient production. CHr (reticulocyte hemoglobin content) <29 pg = iron-restricted erythropoiesis.Mababang reticulocytes = kulang na produksyon. CHr (reticulocyte hemoglobin content) <29 pg = iron-restricted erythropoiesis.Ubos nga reticulocytes = kulang nga produksyon. CHr (reticulocyte hemoglobin content) <29 pg = iron-restricted erythropoiesis. Mababang reticulocytes = kulang a produksyon. CHr (reticulocyte hemoglobin content) <29 pg = iron-restricted erythropoiesis. |
| Serum B12 and folateSerum B12 at folateSerum B12 ug folate Serum B12 at folate | Macrocytic/megaloblastic anemiaMacrocytic/megaloblastic anemiaMacrocytic/megaloblastic anemia Macrocytic/megaloblastic anemia | B12 <200 pg/mL = deficiency. Low folate with megaloblastic picture requires oral folic acid 1–5 mg daily.B12 <200 pg/mL = kakulangan. Mababang folate na may megaloblastic na larawan ay nangangailangan ng oral folic acid 1–5 mg araw-araw.B12 <200 pg/mL = kakulang. Ubos nga folate nga adunay megaloblastic nga hulagway nanginahanglan og oral folic acid 1–5 mg matag adlaw. B12 <200 pg/mL = kakulangan. Mababang folate a atin megaloblastic a larawan ya nangangailangan ning oral folic acid 1–5 mg aldo-aldo. |
| Hemoglobin electrophoresisHemoglobin electrophoresisHemoglobin electrophoresis Hemoglobin electrophoresis | Thalassemia and hemoglobin variantsThalassemia at mga variant ng hemoglobinThalassemia ug mga variant sa hemoglobin Thalassemia at deng variant ning hemoglobin | Essential when microcytic anemia does not respond to iron therapy. Common in Filipino patients — alpha and beta thalassemia trait are prevalent.Mahalaga kapag ang microcytic anemia ay hindi tumutugon sa iron therapy. Karaniwan sa mga pasyenteng Pilipino — ang alpha at beta thalassemia trait ay laganap.Hinungdanon kon ang microcytic anemia dili motubag sa iron therapy. Kasagarang makita sa mga pasyenteng Pilipino — ang alpha ug beta thalassemia trait kaylap. Importante nung ing microcytic anemia ya ali tumutugon king iron therapy. Karaniwan king deng pasyenteng Pilipino — ing alpha at beta thalassemia trait ya laganap. |
| CRP (C-reactive protein) / hsCRPCRP / hsCRPCRP / hsCRP CRP / hsCRP | Inflammation — suppresses iron utilizationPamamaga — pinipigilan ang paggamit ng ironPamamaga — nagpugong sa paggamit sa iron Pamamaga — pinipigilan ing paggamit ning iron | Elevated CRP + low TSAT + high ferritin = anemia of chronic disease / iron-restricted erythropoiesis. IV iron + treat underlying inflammation.Mataas na CRP + mababang TSAT + mataas na ferritin = anemia ng kronikong sakit / iron-restricted erythropoiesis. IV iron + gamutin ang pinagbabatayan na pamamaga.Taas nga CRP + ubos nga TSAT + taas nga ferritin = anemia sa kroniko nga sakit / iron-restricted erythropoiesis. IV iron + tambalon ang nagpapailalom nga pamamaga. Matas a CRP + mababang TSAT + matas a ferritin = anemia ning kronikong sakit / iron-restricted erythropoiesis. IV iron + gamutin ing pinagbabatayan a pamamaga. |
Iron Supplementation — Oral vs IntravenousPagdadagdag ng Iron — Oral kumpara sa IntravenousPagdugang sa Iron — Oral batok sa Intravenous Pagdadagdag ning Iron — Oral kumpara king Intravenous

KDIGO 2026 guidance for adult CKD anemia. Clinical decisions are individualized; the text below gives the criteria and limitations.
- CKD
- Chronic kidney disease
- Hb
- Hemoglobin
- ESA
- Erythropoiesis-stimulating agent
- TSAT
- Transferrin saturation
Oral iron — overviewOral iron — pangkalahatang-ideyaOral iron — kinatibuk-an Oral iron — pangkalahatang-ideya
Oral iron remains the first-line choice for pre-dialysis CKD Stage 1–3 with mild-to-moderate iron deficiency. Absorption is limited in CKD (hepcidin elevation, reduced gastric acid) — typically only 10–15% of the elemental iron dose is absorbed, compared to 25–35% in healthy individuals. Multiple formulations are now available in the Philippines with different elemental iron content, tolerability profiles, and mechanisms of absorption. See comparison table below.Ang oral iron ay nananatiling pangunahing pagpipilian para sa pre-dialysis CKD Stage 1–3 na may banayad hanggang katamtamang kakulangan ng iron. Ang pagsipsip ay limitado sa CKD (pagtaas ng hepcidin, nabawasang gastric acid) — karaniwang 10–15% lamang ng elemental iron dose ang nasipsip, kumpara sa 25–35% sa mga malusog na tao. Maraming formulation ang available na sa Pilipinas na may iba't ibang nilalaman ng elemental iron, profile ng tolerability, at mekanismo ng pagsipsip. Tingnan ang talahanayan ng paghahambing sa ibaba.Ang oral iron nagpabilin nga pangunahing kapilian alang sa pre-dialysis CKD Stage 1–3 nga adunay banayad hangtod katamtamang kakulang sa iron. Ang pagsuyop limitado sa CKD (pagtaas sa hepcidin, nabuwang gastric acid) — kasagarang 10–15% lamang sa elemental iron dose ang nasuyop, kumpara sa 25–35% sa mga malusog nga tawo. Daghang formulation ang available na sa Pilipinas nga adunay lain-laing sulod sa elemental iron, profile sa tolerability, ug mekanismo sa pagsuyop. Tan-awa ang talahanayan sa pagtandi sa ubos. Ing oral iron ya nananatiling pangunahing pagpipilian para king pre-dialysis CKD Stage 1–3 a atin banayad anggang katamtamang kakulangan ning iron. Ing pagsipsip ya limitado king CKD (pagtaas ning hepcidin, nabawasang gastric acid) — karaniwang 10–15% lamang ning elemental iron dose ing nasipsip, kumpara king 25–35% king deng malusog a tao. Dacal a formulation ing available a king Pilipinas a atin iba't ibang nilalaman ning elemental iron, profile ning tolerability, at mekanismo ning pagsipsip. Tingnan ing talahanayan ning paghahambing king ibaba.
IV iron — preferred in hemodialysis; an option in other CKDIV iron — mas pinipili sa hemodialysis; isang opsyon sa ibang CKDIV iron — gipalabi sa hemodialysis; usa ka kapilian sa ubang CKD IV iron — mas pipilinan king hemodialysis; metung a opsyon king aliwa pang CKD
IV iron sucrose is the standard in Philippine dialysis centers, available locally as Ferrofer, Anema, and Ferriscript (all iron sucrose 100 mg/5 mL ampoules — available at Philippine dialysis centers). All are iron sucrose complex formulations and are clinically equivalent for standard dosing. IV iron bypasses absorption barriers and delivers iron directly to storage and bone marrow. In in-center hemodialysis it is generally preferred over oral iron; in non-dialysis CKD it is one option among several and is not automatically superior to a trial of oral iron. In hemodialysis (HD) it is commonly given as 100 mg per session, up to 10 sessions to replace a deficit, then as a scheduled maintenance dose set by your unit and adjusted to your iron tests. Infuse slowly over 15–30 minutes diluted in 100 mL normal saline. Monitor for hypersensitivity reactions — observe patient for 30 minutes post-infusion. Per KDIGO 2026, withhold iron when ferritin >700 ng/mL or TSAT ≥40%, and temporarily suspend IV iron during active systemic infection (ferritin is also falsely raised by inflammation).Ang IV iron sucrose ang karaniwang ginagamit sa mga dialysis center sa Pilipinas, available nang lokal bilang Ferrofer, Anema, at Ferriscript (lahat ay iron sucrose 100 mg/5 mL ampoule). Lahat ay naglalaman ng iron sucrose complex at clinically equivalent para sa karaniwang dosis. Ang IV iron ay lumalampas sa mga hadlang sa pagsipsip at naghahatid ng iron nang direkta sa imbakan at bone marrow. Sa in-center hemodialysis, karaniwang mas pinipili kaysa oral iron; sa non-dialysis CKD ito ay isa lamang sa mga opsyon at hindi awtomatikong mas mahusay kaysa subok ng oral iron. Sa HD, karaniwang ibinibigay ito bilang 100 mg bawat session, hanggang 10 session upang punan ang kakulangan, at pagkatapos ay isang nakatakdang maintenance na dosis na itinatakda ng inyong unit at inaayon sa iyong iron tests. Mag-infuse nang dahan-dahan sa loob ng 15–30 minuto na natunaw sa 100 mL normal saline. Bantayan ang mga reaksyon ng hypersensitivity — obserbahan ang pasyente sa loob ng 30 minuto pagkatapos ng infusion. Ayon sa KDIGO 2026, pigilan ang iron kapag ferritin >700 ng/mL o TSAT ≥40%, at pansamantalang ihinto ang IV iron sa panahon ng aktibong systemic infection (mataas din nang mali ang ferritin dahil sa pamamaga).Ang IV iron sucrose kasagarang gigamit sa mga dialysis center sa Pilipinas, available nang lokal isip Ferrofer, Anema, ug Ferriscript (tanan iron sucrose 100 mg/5 mL ampoule). Tanan adunay iron sucrose complex ug clinically equivalent alang sa standard nga dosis. Ang IV iron milabang sa mga babag sa pagsuyop ug naghatod sa iron direkta sa imbakan ug bone marrow. Sa in-center hemodialysis sagad gipalabi kaysa oral iron; sa non-dialysis CKD kini usa lamang ka kapilian ug dili awtomatikong mas maayo kaysa pagsulay sa oral iron. Sa HD, kasagaran kini ihatag isip 100 mg matag session, hangtod 10 ka session aron pun-on ang kakulang, unya usa ka naka-iskedyul nga maintenance nga dosis nga gitakda sa inyong unit ug gipahaom sa imong iron tests. Mag-infuse nga hinay sulod sa 15–30 minuto nga natunaw sa 100 mL normal saline. Bantayan ang mga reaksyon sa hypersensitivity — obserbahan ang pasyente sulod sa 30 minuto human sa infusion. Sumala sa KDIGO 2026, pugngan ang iron kon ferritin >700 ng/mL o TSAT ≥40%, ug temporaryong ihunong ang IV iron sa panahon sa aktibong systemic infection (ang ferritin sayop usab nga mosaka tungod sa pamamaga). Ing IV iron sucrose ing karaniwang gagamitan king deng dialysis center king Pilipinas, available nang lokal bilang Ferrofer, Anema, at Ferriscript (amin ya iron sucrose 100 mg/5 mL ampoule). Amin ya naglalaman ning iron sucrose complex at clinically equivalent para king karaniwang dosis. Ing IV iron ya lumalampas king deng hadlang king pagsipsip at naghahatid ning iron nang direkta king imbakan at bone marrow. King in-center hemodialysis, karaniwang mas pipilinan kaysa oral iron; king non-dialysis CKD ya metung ne mu king deng opsyon at ali awtomatikong mas mayap kaysa subuk ning oral iron. King HD, karaniwang ibie ya bilang 100 mg bawat session, anggang 10 session para punan ing kakulangan, kaybat metung a nakatakdang maintenance a dosis a itakda ning unit yu at iayun king iron tests mu. Mag-infuse nang dahan-dahan king loob ning 15–30 minuto a natunaw king 100 mL normal saline. Bantayan ing deng reaksyon ning hypersensitivity — obserbahan ing pasyente king loob ning 30 minuto kapabanuan ning infusion. Base king KDIGO 2026, pigilan ing iron nung ferritin >700 ng/mL o TSAT ≥40%, at pansamantalang ihinto ing IV iron king panahon ning aktibong systemic infection (matas mu naman nang mali ing ferritin uli ning pamamaga).
Oral Iron Formulations — New vs. ConventionalMga Formulation ng Oral Iron — Bago kumpara sa TradisyonalMga Formulation sa Oral Iron — Bag-o batok sa Tradisyonal Deng Formulation ning Oral Iron — Bago kumpara king Tradisyonal
Not all oral iron supplements are equal. Conventional ferrous sulfate is inexpensive but poorly tolerated and poorly absorbed in CKD. Newer formulations — sucrosomial iron (Sideral) and liposomal/ferric pyrophosphate (Pelamis) — offer higher bioavailability, significantly fewer GI side effects, and novel absorption pathways that partially bypass hepcidin blockade.Hindi lahat ng oral iron supplement ay pantay. Ang conventional ferrous sulfate ay mura ngunit mahirap tiisin at mahirap masipsip sa CKD. Ang mga bagong formulation — sucrosomial iron (Sideral) at liposomal/ferric pyrophosphate (Pelamis) — ay nag-aalok ng mas mataas na bioavailability, mas kaunting GI side effects, at mga bagong landas ng pagsipsip na bahagyang lumalampas sa hepcidin blockade.Dili tanan nga oral iron supplement managsama. Ang conventional ferrous sulfate barato apan lisod tiiron ug lisod masuyop sa CKD. Ang mga bag-ong formulation — sucrosomial iron (Sideral) ug liposomal/ferric pyrophosphate (Pelamis) — nagtanyag og mas taas nga bioavailability, labi ka gamay nga GI side effects, ug mga bag-ong dalan sa pagsuyop nga bahin nga milabang sa hepcidin blockade. Ali amin ning oral iron supplement ya pantay. Ing conventional ferrous sulfate ya mura ngarud mahirap tiisin at mahirap masipsip king CKD. Ing deng bagong formulation — sucrosomial iron (Sideral) at liposomal/ferric pyrophosphate (Pelamis) — ya nag-aalok ning mas matas a bioavailability, mas kaunting GI side effects, at deng bagong landas ning pagsipsip a bahagyang lumalampas king hepcidin blockade.
| FormulationFormulationFormulation Formulation | Brand (PH)Brand (PH)Brand (PH) Brand (PH) | Elemental FeElemental FeElemental Fe Elemental Fe | Absorption mechanismMekanismo ng pagsipsipMekanismo sa pagsuyop Mekanismo ning pagsipsip | GI tolerabilityGI tolerabilityGI tolerability GI tolerability | CKD rolePapel sa CKDPapel sa CKD Papel king CKD |
|---|---|---|---|---|---|
| Ferrous sulfate (FeSO₄) | Feosol, Ferobin, generics | 65 mg per 325 mg tab | DMT-1 transporter (duodenum). Requires acidic gastric environment. Blocked by hepcidin and inflammation.DMT-1 transporter (duodenum). Nangangailangan ng maasim na kapaligiran sa tiyan. Hinahadlangan ng hepcidin at pamamaga.DMT-1 transporter (duodenum). Nanginahanglan og acidic nga kapaligiran sa tiyan. Gipugngan sa hepcidin ug pamamaga. DMT-1 transporter (duodenum). Nangangailangan ning maasim a kapaligiran king tiyan. Hinahadlangan ning hepcidin at pamamaga. | PoorMahirapDili maayo Mahirap — constipation, nausea, black stools common. GI side effects lead to non-adherence in ~30–40%.constipation, pagduduwal, itim na dumi ay karaniwan. Ang GI side effects ay nagdudulot ng hindi pagsunod sa ~30–40%.constipation, pagduwal, itom nga tae kasagarang mahitabo. Ang GI side effects nagdala sa dili pagsunod sa ~30–40%. constipation, pagduduwal, itim a dumi ya karaniwan. Ing GI side effects ya nagdudulot ning ali pagsunod king ~30–40%. | First-line for many people with mild deficiency. Absorption can be lower in advanced CKD, but a trial is still reasonable outside hemodialysis. Inexpensive.Pangunahing pagpipilian para sa marami na may banayad na kakulangan. Maaaring mas mababa ang pagsipsip sa advanced CKD, ngunit makatwiran pa ring subukan kung hindi naka-hemodialysis. Mura.Pangunahing kapilian alang sa daghan nga may banayad nga kakulang. Mahimong mas ubos ang pagsuyop sa advanced CKD, apan makatarunganon gihapon ang pagsulay kon dili nag-hemodialysis. Barato. Pangunahing pagpipilian para king dakal a atin banayad a kakulangan. Malyaring mas mababa ing pagsipsip king advanced CKD, oneng makatwiran ya pa mu ing subuk nung ali ka naka-hemodialysis. Mura. |
| Ferrous gluconate / fumarate | Fergon, Ferro-folic generics | 36 mg (gluconate) / 33 mg (fumarate) per tab | Same DMT-1 pathway as FeSO₄. Lower elemental iron per dose than sulfate.Parehong DMT-1 pathway gaya ng FeSO₄. Mas mababang elemental iron bawat dosis kaysa sulfate.Pareho nga DMT-1 pathway sama sa FeSO₄. Mas ubos nga elemental iron sa matag dosis kaysa sulfate. Parehong DMT-1 pathway gaya ning FeSO₄. Mas mababang elemental iron bawat dosis kaysa sulfate. | ModerateKatamtamanKatamtaman Katamtaman — slightly better tolerated than sulfate due to lower elemental iron per dose.bahagyang mas madaling tiisin kaysa sulfate dahil sa mas mababang elemental iron bawat dosis.gamay nga mas sayon tiiron kaysa sulfate tungod sa mas ubos nga elemental iron sa matag dosis. bahagyang mas madaling tiisin kaysa sulfate dahil king mas mababang elemental iron bawat dosis. | Alternative to FeSO₄ when GI side effects are dose-limiting. Comparable efficacy.Alternatibo sa FeSO₄ kapag ang GI side effects ay dose-limiting. Katulad na bisa.Alternatibo sa FeSO₄ kon ang GI side effects dose-limiting. Katumbas nga epekto. Alternatibo king FeSO₄ nung ing GI side effects ya dose-limiting. Katulad a bisa. |
| Sucrosomial iron (ferric pyrophosphate encapsulated in phospholipid + sucrose ester matrix) |
Sideral (Pharma Nord / local distributors) 30 mg elemental Fe capsule |
30 mg per capsule | Absorbed via both DMT-1 and a novel transcellular pathway through enterocytes — partially bypasses the hepcidin-DMT1 blockade seen in CKD. Does not require gastric acid activation.Nasisisip sa pamamagitan ng parehong DMT-1 at isang bagong transcellular pathway sa pamamagitan ng mga enterocyte — bahagyang lumalampas sa hepcidin-DMT1 blockade na nakikita sa CKD. Hindi nangangailangan ng gastric acid activation.Nasuyop pinaagi sa DMT-1 ug usa ka bag-ong transcellular pathway pinaagi sa mga enterocyte — bahin nga milabang sa hepcidin-DMT1 blockade nga makita sa CKD. Wala nagkinahanglan og gastric acid activation. Nasisisip king pamamagitan ning parehong DMT-1 at metung a bagong transcellular pathway king pamamagitan ning deng enterocyte — bahagyang lumalampas king hepcidin-DMT1 blockade a nakikita king CKD. Ali nangangailangan ning gastric acid activation. | GoodMabutiMaayo Mabuti — phospholipid matrix protects GI mucosa. Significantly fewer side effects than FeSO₄. Can be taken with food.ang phospholipid matrix ay nagpoprotekta sa GI mucosa. Mas kaunting side effects kaysa FeSO₄. Maaaring inumin kasama ang pagkain.ang phospholipid matrix nagpanalipod sa GI mucosa. Labi ka gamay nga side effects kaysa FeSO₄. Mahimong inumon uban sa pagkaon. ing phospholipid matrix ya nagpoprotekta king GI mucosa. Mas kaunting side effects kaysa FeSO₄. Maaaring inumin kasama ing pamangan. | An option in non-dialysis CKD when standard iron is not tolerated. In a small randomized controlled trial (RCT) it raised hemoglobin with fewer side effects, though less than IV iron did. Higher cost than FeSO₄.Opsyon sa non-dialysis CKD kapag hindi kayang tiisin ang karaniwang iron. Sa isang maliit na RCT, itinaas nito ang hemoglobin nang may mas kaunting side effects, bagaman mas kaunti kaysa sa IV iron. Mas mataas na gastos kaysa FeSO₄.Kapilian sa non-dialysis CKD kon dili matiiron ang kasagarang iron. Sa usa ka gamay nga RCT, gipataas niini ang hemoglobin nga may mas gamay nga side effects, bisan mas gamay kaysa sa IV iron. Mas taas nga gasto kaysa FeSO₄. Opsyon king non-dialysis CKD nung ali kayang tiisin ing karaniwang iron. King metung a malating RCT, pepatas na ing hemoglobin a mas kakaunti ing side effects, oneng mas kakaunti kesa king IV iron. Mas matas a gastos kaysa FeSO₄. |
| Ferric pyrophosphate citrate — oral / dialysate (liposomal iron formulation) |
Pelamis (oral sachets) Note: Triferic (dialysate FPC) is a related but distinct IV formulation — not the same as oral Pelamis |
Variable by sachet formulation — confirm on package insert | Liposomal encapsulation delivers ferric iron directly to enterocyte membrane — absorbed via a non-DMT1 pathway. Highly resistant to hepcidin blockade. Stable at neutral pH — does not require gastric acid.Ang liposomal encapsulation ay naghahatid ng ferric iron nang direkta sa enterocyte membrane — nasisisip sa pamamagitan ng non-DMT1 pathway. Lubos na lumalaban sa hepcidin blockade. Matatag sa neutral pH — hindi nangangailangan ng gastric acid.Ang liposomal encapsulation naghatod sa ferric iron direkta sa enterocyte membrane — nasuyop pinaagi sa non-DMT1 pathway. Labi ka batok sa hepcidin blockade. Lig-on sa neutral pH — wala nagkinahanglan og gastric acid. Ing liposomal encapsulation ya naghahatid ning ferric iron nang direkta king enterocyte membrane — nasisisip king pamamagitan ning non-DMT1 pathway. Lubos a lumalaban king hepcidin blockade. Matatag king neutral pH — ali nangangailangan ning gastric acid. | ExcellentNapakahusayLabing maayo Napakahusay — minimal GI side effects due to liposomal protection. Can be taken at any time, with or without food.minimal na GI side effects dahil sa liposomal protection. Maaaring inumin anumang oras, may pagkain man o wala.minimal nga GI side effects tungod sa liposomal protection. Mahimong inumon bisan unsang oras, uban o walay pagkaon. minimal a GI side effects dahil king liposomal protection. Maaaring inumin anumang oras, atin pamangan man o ala. | An alternative oral formulation for CKD patients who cannot tolerate conventional iron or have significant hepcidin-mediated absorption failure. Local availability: verify current FDA-PH (Food and Drug Administration Philippines) registration status before prescribing. Higher cost. Evidence in CKD is still limited.Alternatibong oral formulation para sa mga pasyenteng may CKD na hindi kayang tiisin ang conventional iron o may malaking hepcidin-mediated absorption failure. Lokal na availability: i-verify ang kasalukuyang FDA-PH registration status bago mag-reseta. Mas mataas na gastos. Limitado pa ang ebidensya sa CKD.Alternatibong oral formulation alang sa mga pasyente nga may CKD nga dili makatiis sa conventional iron o adunay dakong hepcidin-mediated absorption failure. Lokal nga availability: i-verify ang kasamtangang FDA-PH registration status sa wala pa mag-reseta. Mas taas nga gasto. Limitado pa ang ebidensya sa CKD. Alternatibong oral formulation para king deng pasyenteng atin CKD a ali kayang tiisin ing conventional iron o atin malaking hepcidin-mediated absorption failure. Lokal a availability: i-verify ing kasalukuyang FDA-PH registration status bago mag-reseta. Mas matas a gastos. Limitado pa ing ebidensya king CKD. |
| Iron sucrose IV (parenteral — reference standard) |
Ferrofer, Anema, Ferriscript | 100 mg / 5 mL ampoule (20 mg/mL) | Direct IV delivery — 100% bioavailable. No GI absorption required. Bypasses all hepcidin-mediated barriers. Taken up by reticuloendothelial system and released to transferrin.Direktang IV delivery — 100% bioavailable. Hindi kailangan ng GI absorption. Lumalampas sa lahat ng hepcidin-mediated barriers. Kinukuha ng reticuloendothelial system at inilalabas sa transferrin.Direktang IV delivery — 100% bioavailable. Wala kinahanglana nga GI absorption. Milabang sa tanan nga hepcidin-mediated barriers. Gikuha sa reticuloendothelial system ug gipagawas sa transferrin. Direktang IV delivery — 100% bioavailable. Ali kailangan ning GI absorption. Lumalampas king amin ning hepcidin-mediated barriers. Kinukuha ning reticuloendothelial system at inilalabas king transferrin. | N/A (IV) — No GI side effects. Hypersensitivity reaction risk (<1%); observe 30 min post-infusion.Walang GI side effects. Panganib ng hypersensitivity reaction (<1%); obserbahan ng 30 min pagkatapos ng infusion.Walay GI side effects. Peligro sa hypersensitivity reaction (<1%); obserbahan og 30 min human sa infusion. Alang GI side effects. Panganib ning hypersensitivity reaction (<1%); obserbahan ning 30 min kapabanuan ning infusion. | Preferred in hemodialysis, and when oral iron fails or is not tolerated. The fastest way to refill iron stores. Given in a dialysis unit or clinic.Mas pinipili sa hemodialysis, at kapag hindi gumana o hindi matiis ang oral iron. Pinakamabilis na paraan upang punan ang imbakan ng iron. Ibinibigay sa dialysis unit o klinika.Gipalabi sa hemodialysis, ug kon dili molihok o dili matiiron ang oral iron. Labing paspas nga paagi sa pagpuno sa imbakan sa iron. Ihatag sa dialysis unit o klinika. Mas pipilinan king hemodialysis, at nung ali gumana o ali matiis ing oral iron. Pekamabilis a paralan para punan ing imbakan ning iron. Ibie king dialysis unit o klinika. |
Practical prescribing guidance — choosing the right oral iron in CKDPraktikal na gabay sa pag-reseta — pagpili ng tamang oral iron sa CKDPraktikal nga giya sa pag-reseta — pagpili sa husto nga oral iron sa CKD Praktikal a gabay king pag-reseta — pagpili ning tamang oral iron king CKD
- CKD Stage 1–2, mild deficiency, no inflammation:CKD Stage 1–2, banayad na kakulangan, walang pamamaga:CKD Stage 1–2, banayad nga kakulang, walay pamamaga: CKD Stage 1–2, banayad a kakulangan, alang pamamaga: Ferrous sulfate 325 mg OD–BID on empty stomach + calamansi juice. Inexpensive, effective if hepcidin not elevated.Ferrous sulfate 325 mg OD–BID sa walang laman na tiyan + katas ng calamansi. Mura, epektibo kung hindi mataas ang hepcidin.Ferrous sulfate 325 mg OD–BID sa walay sulod nga tiyan + katas sa calamansi. Barato, epektibo kon dili taas ang hepcidin. Ferrous sulfate 325 mg OD–BID king alang laman a tiyan + katas ning calamansi. Mura, epektibo nung ali matas ing hepcidin.
- CKD Stage 2–4, GI intolerance to FeSO₄ or suboptimal response:CKD Stage 2–4, hindi matiisin ang FeSO₄ sa GI o suboptimal na tugon:CKD Stage 2–4, dili matiiron ang FeSO₄ sa GI o suboptimal nga tubag: CKD Stage 2–4, ali matiisin ing FeSO₄ king GI o suboptimal a tugon: Sideral (sucrosomial iron) 1 cap OD–BID with food. Better tolerability, partially bypasses hepcidin, suitable for patients who cannot tolerate conventional iron.Sideral (sucrosomial iron) 1 cap OD–BID kasama ang pagkain. Mas madaling tiisin, bahagyang lumalampas sa hepcidin, angkop para sa mga pasyenteng hindi makakatiisin ng conventional iron.Sideral (sucrosomial iron) 1 cap OD–BID uban sa pagkaon. Mas sayon tiiron, bahin nga milabang sa hepcidin, angay alang sa mga pasyente nga dili makatiis sa conventional iron. Sideral (sucrosomial iron) 1 cap OD–BID kasama ing pamangan. Mas madaling tiisin, bahagyang lumalampas king hepcidin, angkop para king deng pasyenteng ali makakatiisin ning conventional iron.
- CKD Stage 3–4, significant hepcidin elevation, absorption failure:CKD Stage 3–4, makabuluhang pagtaas ng hepcidin, kabiguan sa pagsipsip:CKD Stage 3–4, dakong pagtaas sa hepcidin, pagkapakyas sa pagsuyop: CKD Stage 3–4, makabuluhang pagtaas ning hepcidin, kabiguan king pagsipsip: Consider Pelamis (liposomal FPC) sachets — verify local FDA-PH availability before prescribing.Isaalang-alang ang Pelamis (liposomal FPC) sachets — i-verify ang lokal na FDA-PH availability bago mag-reseta.Konsiderahon ang Pelamis (liposomal FPC) sachets — i-verify ang lokal nga FDA-PH availability sa wala pa mag-reseta. Isaalang-alang ing Pelamis (liposomal FPC) sachets — i-verify ing lokal a FDA-PH availability bago mag-reseta.
- Hemodialysis patients:Mga pasyenteng nasa hemodialysis:Mga pasyente nga nag-hemodialysis: Deng pasyenteng nasa hemodialysis: IV iron sucrose (Ferrofer, Anema, or Ferriscript) is generally preferred over oral iron in in-center HD — ongoing dialysis losses and hepcidin-driven iron-restricted erythropoiesis limit oral absorption. Individualized exceptions (prior reactions, availability, cost, patient preference) still apply.Ang IV iron sucrose (Ferrofer, Anema, o Ferriscript) ay karaniwang mas pinipili kaysa oral iron sa in-center HD — nililimitahan ng patuloy na pagkawala sa dialysis at ng hepcidin-driven na iron-restricted erythropoiesis ang oral na pagsipsip. May natatanging mga eksepsyon (dating reaksyon, availability, gastos, kagustuhan ng pasyente).Ang IV iron sucrose (Ferrofer, Anema, o Ferriscript) sagad gipalabi kaysa oral iron sa in-center HD — ang padayon nga pagkawala sa dialysis ug ang hepcidin-driven nga iron-restricted erythropoiesis naglimit sa oral nga pagsuyop. Adunay indibidwal nga mga eksepsyon (kaniadto nga reaksyon, availability, gasto, gusto sa pasyente). Ing IV iron sucrose (Ferrofer, Anema, o Ferriscript) ya karaniwang mas pipilinan kaysa oral iron king in-center HD — nililimitahan ning tuluy-tuluy a pangawala king dialysis at ning hepcidin-driven a iron-restricted erythropoiesis ing oral a pagsipsip. Atin natatanging deng eksepsyon (dating reaksyon, availability, gastu, kaburian ning pasyente).
- CKD not on dialysis (including G3b–G5):CKD na hindi nasa dialysis (kabilang ang G3b–G5):CKD nga wala sa dialysis (lakip ang G3b–G5): CKD a ali nasa dialysis (kayabe ing G3b–G5): Either oral or IV iron can be reasonable — the route is individualized to severity, prior response, tolerance, availability, cost, venous access, and preference. Oral iron is not uniformly ineffective in G3b–G5; a trial is appropriate for many, with IV iron reserved for intolerance, poor response, or more severe deficiency.Alinman sa oral o IV iron ay maaaring makatwiran — isinasapersonal ang ruta batay sa tindi, dating tugon, tiyaga, availability, gastos, venous access, at kagustuhan. Ang oral iron ay hindi pare-parehong hindi epektibo sa G3b–G5; angkop ang subok para sa marami, at nakalaan ang IV iron para sa hindi pagtitiis, mahinang tugon, o mas malubhang kakulangan.Bisan asa sa oral o IV iron makatarunganon — gipahiangay ang ruta sa kagrabe, kaniadto nga tubag, pagkamaantoson, availability, gasto, venous access, ug gusto. Ang oral iron dili managsama nga dili epektibo sa G3b–G5; angay ang usa ka pagsulay alang sa daghan, ug ang IV iron gitagana alang sa dili pagkamaantoson, huyang nga tubag, o mas grabe nga kakulang. Nokarin man king oral o IV iron ya malyaring makatwiran — me-personalize ing ruta base king tindi, dating tugon, tiyaga, availability, gastu, venous access, at kaburian. Ing oral iron ya ali parehong ali epektibo king G3b–G5; angkop ing subuk para king dakal, at nakalaan ing IV iron para king ali pamagtiis, mahinang tugon, o mas malubhang kakulangan.
- Pause IV iron during active systemic infectionPansamantalang ihinto ang IV iron habang may aktibong systemic infectionIhunong sa makadiyot ang IV iron samtang adunay aktibong systemic infection Pansamantalang ihinto ing IV iron kabang atin aktibong systemic infection — see alert below.tingnan ang alerto sa ibaba.tan-awa ang alerto sa ubos. tingnan ing alerto king ibaba.
Do not give IV iron during active infectionHuwag magbigay ng IV iron sa panahon ng aktibong impeksyonAyaw hatagi og IV iron sa panahon sa aktibong impeksyon Eka magbigay ning IV iron king panahon ning aktibong impeksyon
IV iron should be withheld during active bacterial infection — bacteria thrive on free iron, and IV iron administration during sepsis or bacteremia worsens outcomes. KDIGO 2026 suggests considering a temporary pause; your team restarts iron once the infection is under control.Ang IV iron ay dapat pigilan sa panahon ng aktibong impeksyon sa bakterya — ang mga bakterya ay lumalaki sa libreng iron, at ang pagbibigay ng IV iron sa panahon ng sepsis o bacteremia ay nagpapalala ng mga resulta. Iminumungkahi ng KDIGO 2026 na isaalang-alang ang pansamantalang paghinto; ibabalik ng iyong team ang iron kapag kontrolado na ang impeksyon.Ang IV iron kinahanglan nga pugngan sa panahon sa aktibong impeksyon sa bakterya — ang mga bakterya naglambo sa libre nga iron, ug ang paghatag sa IV iron sa panahon sa sepsis o bacteremia nagpagrabe sa mga resulta. Gisugyot sa KDIGO 2026 nga ikonsiderar ang temporaryong paghunong; ibalik sa imong team ang iron kon kontrolado na ang impeksyon. Ing IV iron ya dapat pigilan king panahon ning aktibong impeksyon king bakterya — ing deng bakterya ya lumalaki king libreng iron, at ing pagbibigay ning IV iron king panahon ning sepsis o bacteremia ya nagpapalala ning deng resulta. Ipayu ning KDIGO 2026 ing pansamantalang pamaghinto; ibalik na ning team mu ing iron nung kontrolado na ing impeksyon.
ESA Therapy — Replacing the Kidney's SignalESA Therapy — Pagpapalit sa Signal ng BatoESA Therapy — Pagpuli sa Signal sa Kidney ESA Therapy — Pagpapalit king Signal ning Batu

KDIGO 2026 guidance for adult CKD anemia. Clinical decisions are individualized; the text below gives the criteria and limitations.
- CKD
- Chronic kidney disease
- Hb
- Hemoglobin
- ESA
- Erythropoiesis-stimulating agent
- TSAT
- Transferrin saturation
Before starting an ESA, reversible causes are corrected first — iron deficiency, infection or inflammation, B12/folate deficiency, and blood loss. When those are addressed and hemoglobin is still low, erythropoiesis-stimulating agents (ESAs) may be considered. There is no single hemoglobin number that triggers ESA in every population; the decision is individualized (symptoms, how fast hemoglobin is falling, wish to avoid transfusion, transplant candidacy, and risks such as cancer, stroke, or clots) and made through shared decision-making with your nephrologist. The goal is to use the lowest effective dose to relieve symptoms and reduce the need for transfusion — not to normalize hemoglobin.Bago simulan ang ESA, unang itinatama ang mga nababawi na sanhi — kakulangan sa iron, impeksyon o pamamaga, kakulangan sa B12/folate, at pagkawala ng dugo. Kapag natugunan ang mga ito at mababa pa rin ang hemoglobin, maaaring isaalang-alang ang erythropoiesis-stimulating agents (ESA). Walang iisang numero ng hemoglobin na nagsisimula ng ESA sa bawat populasyon; isinasapersonal ang desisyon (sintomas, bilis ng pagbaba ng hemoglobin, hangaring iwasan ang transfusion, pagiging kandidato sa transplant, at mga panganib tulad ng kanser, stroke, o pamumuo) sa pamamagitan ng shared decision-making kasama ang inyong nephrologist. Layunin ang pinakamababang epektibong dosis upang mapawi ang sintomas at bawasan ang pangangailangan sa transfusion — hindi ang gawing normal ang hemoglobin.Sa dili pa magsugod og ESA, unahon pagtul-id ang mga mabalik nga hinungdan — kakulang sa iron, impeksyon o pamamaga, kakulang sa B12/folate, ug pagkawala sa dugo. Kon masulbad kini ug ubos gihapon ang hemoglobin, mahimong konsiderahon ang erythropoiesis-stimulating agents (ESA). Walay usa ka numero sa hemoglobin nga magsugod og ESA sa matag populasyon; ang desisyon gipahiangay (sintomas, kakusog sa pag-ubos sa hemoglobin, tinguha nga malikayan ang transfusion, pagka-kandidato sa transplant, ug mga peligro sama sa kanser, stroke, o pamuo) pinaagi sa shared decision-making uban sa inyong nephrologist. Ang tumong mao ang paggamit sa labing ubos nga epektibong dosis aron mahupay ang sintomas ug makunhod ang panginahanglan sa transfusion — dili aron himoong normal ang hemoglobin. Bayu simulan ing ESA, mumuna metatama ing deng mababawi a sanhi — kakulangan king iron, impeksyon o pamamaga, kakulangan king B12/folate, at pangawala ning daya. Nung metugunan ne deti at mababa pamu ing hemoglobin, malyaring isaalang-alang ing erythropoiesis-stimulating agents (ESA). Alang metung a numeru ning hemoglobin a magsimula ning ESA king balang populasyon; me-personalize ing desisyon (sintomas, bilis ning pamababa ning hemoglobin, kaburian a iwasan ing transfusion, pamagkandidato king transplant, at deng panganib anti ing kanser, stroke, o pamumu) king pamamagitan ning shared decision-making kayabe ing inyu nephrologist. Ing layunin ya gamitan ing pekamababang epektibong dosis para mapawi ing sintomas at bawasan ing pangangailangan king transfusion — ali ing gawang normal ing hemoglobin.
Iron first — alwaysIron muna — palagiIron una — kanunay Iron muna — palagi
ESA therapy without adequate iron stores is ineffective and wasteful — the bone marrow needs iron to build hemoglobin in every new red cell. So iron status should be assessed and optimized before starting or increasing an ESA. The exact ferritin and TSAT figures used differ by population (hemodialysis units are managed differently from non-dialysis CKD), so treat them as thresholds to interpret with your nephrologist, not as fixed automatic orders.Ang ESA therapy nang walang sapat na imbakan ng iron ay hindi epektibo at sayang — kailangan ng bone marrow ang iron upang bumuo ng hemoglobin sa bawat bagong pulang selula. Kaya dapat suriin at i-optimize ang katayuan ng iron bago simulan o taasan ang ESA. Naiiba ang eksaktong bilang ng ferritin at TSAT ayon sa populasyon (magkaiba ang pamamahala sa hemodialysis at sa non-dialysis CKD), kaya ituring ang mga ito bilang threshold na binibigyang-kahulugan kasama ang inyong nephrologist, hindi bilang nakapirming awtomatikong utos.Ang ESA therapy nga walay igo nga imbakan sa iron dili epektibo ug sayang — ang bone marrow nanginahanglan og iron aron magtukod og hemoglobin sa matag bag-ong pulang selula. Busa kinahanglan susihon ug i-optimize ang kahimtang sa iron sa dili pa magsugod o magdugang sa ESA. Lahi ang eksaktong numero sa ferritin ug TSAT matag populasyon (lahi ang pagdumala sa hemodialysis ug sa non-dialysis CKD), busa isipa kini nga mga threshold nga hubaron uban sa inyong nephrologist, dili nga pihong awtomatikong mando. Ing ESA therapy nang alang sapat a imbakan ning iron ya ali epektibo at sayang — kailangan ning bone marrow ing iron para bumuo ning hemoglobin king balang bagong pulang selula. Kaya dapat suriin at i-optimize ing katayuan ning iron bayu simulan o taasan ing ESA. Miyayaliwa ing eksaktong bilang ning ferritin at TSAT base king populasyon (miyayaliwa ing pamamahala king hemodialysis at king non-dialysis CKD), kaya ituring la deti bilang threshold a bibiyang-kahulugan kayabe ing inyu nephrologist, ali bilang nakapirming awtomatikong utos.
Starting dose and routePanimulang dosis at rutaSinugdanan nga dosis ug ruta Panimulang dosis at ruta
Epoetin alfa — available in the Philippines as Eprex (Janssen) and Eposino (Goodfellow) — is the standard first-line ESA. Dose: 4,000 IU subcutaneously 2–3 times per week (or IV during dialysis). Recormon (Roche) is epoetin beta — a distinct molecular form available in 2,000 IU, 5,000 IU, and 10,000 IU prefilled syringes — and is also used in the Philippines but is not epoetin alfa. Both alpha and beta forms stimulate the same EPO receptor and have comparable clinical efficacy at equivalent doses; however they are not interchangeable unit-for-unit — confirm the specific agent and dose with your nephrologist. Darbepoetin alfa has a longer half-life and can be given weekly or every 2 weeks at lower injection frequency. Start low and titrate — overshoot above 115 g/L increases cardiovascular risk and thrombosis.Epoetin alfa — available sa Pilipinas bilang Eprex (Janssen) at Eposino (Goodfellow) — ang pamantayang pangunahing ESA. Dosis: 4,000 IU subcutaneously 2–3 beses bawat linggo (o IV sa panahon ng dialysis). Ang Recormon (Roche) ay epoetin beta — isang natatanging molecular form na available sa 2,000 IU, 5,000 IU, at 10,000 IU prefilled syringe — at ginagamit din sa Pilipinas ngunit hindi epoetin alfa. Ang parehong alpha at beta form ay nagpapasigla ng parehong EPO receptor at may katulad na klinikal na bisa sa katumbas na dosis; gayunpaman hindi sila maaaring palitan nang unit-for-unit — kumpirmahin ang tiyak na agent at dosis sa inyong nephrologist. Ang darbepoetin alfa ay may mas matagal na half-life at maaaring ibigay lingguhan o bawat 2 linggo sa mas mababang dalas ng iniksyon. Magsimula nang mababa at mag-titrate — ang paglampas sa itaas ng 115 g/L ay nagpapataas ng cardiovascular risk at thrombosis.Epoetin alfa — available sa Pilipinas isip Eprex (Janssen) ug Eposino (Goodfellow) — ang pamantayang pangunahing ESA. Dosis: 4,000 IU subcutaneously 2–3 ka beses sa matag semana (o IV sa panahon sa dialysis). Ang Recormon (Roche) mao ang epoetin beta — usa ka lain nga molecular form nga available sa 2,000 IU, 5,000 IU, ug 10,000 IU prefilled syringe — ug gigamit usab sa Pilipinas apan dili epoetin alfa. Ang alpha ug beta form nagdasig sa pareho nga EPO receptor ug adunay katumbas nga klinikal nga epekto sa katumbas nga dosis; bisan pa dili sila mapuli sa unit-for-unit — kumpirmahon ang espesipikong agent ug dosis sa inyong nephrologist. Ang darbepoetin alfa adunay mas taas nga half-life ug mahimong ihatag matag semana o matag 2 ka semana sa mas ubos nga dalas sa iniksyon. Magsugod nga ubos ug mag-titrate — ang pagsabaw sa ibabaw sa 115 g/L nagpataas sa cardiovascular risk ug thrombosis. Epoetin alfa — available king Pilipinas bilang Eprex (Janssen) at Eposino (Goodfellow) — ing pamantayang pangunahing ESA. Dosis: 4,000 IU subcutaneously 2–3 beses bawat lutu (o IV king panahon ning dialysis). Ing Recormon (Roche) ya epoetin beta — metung a natatanging molecular form a available king 2,000 IU, 5,000 IU, at 10,000 IU prefilled syringe — at ginagamit din king Pilipinas ngarud ali epoetin alfa. Ing parehong alpha at beta form ya nagpapasigla ning parehong EPO receptor at atin katulad a klinikal a bisa king katumbas a dosis; gayunpaman ali sila maaaring palitan nang unit-for-unit — kumpirmahin ing tiyak a agent at dosis king inyu nephrologist. Ing darbepoetin alfa ya atin mas matagal a half-life at maaaring ibigay lingguhan o bawat 2 lutu king mas mababang dalas ning iniksyon. Magsimula nang mababa at mag-titrate — ing paglampas king itaas ning 115 g/L ya nagpapataas ning cardiovascular risk at thrombosis.
Hemoglobin monitoring and targetPagmamasid sa hemoglobin at targetPagbantay sa hemoglobin ug target Pagmamasid king hemoglobin at target
Check hemoglobin regularly and use the lowest effective ESA dose. KDIGO 2026 advises against using ESAs to maintain hemoglobin at or above 115 g/L; if hemoglobin rises by more than 10 g/L in 2–4 weeks or nears 115 g/L, the dose is usually reduced rather than stopped; it may be paused if hemoglobin goes above 115 g/L. Raising hemoglobin into the normal range with ESAs has not been shown to improve heart or kidney outcomes and is linked to more strokes and heart attacks (CHOIR, TREAT trials). The aim is to ease symptoms and avoid transfusion, not to reach a "normal" number.Regular na suriin ang hemoglobin at gamitin ang pinakamababang epektibong dosis ng ESA. Nagpapayo ang KDIGO 2026 laban sa paggamit ng ESA upang panatilihin ang hemoglobin sa 115 g/L o mas mataas; kung tumaas ang hemoglobin nang higit sa 10 g/L sa loob ng 2–4 na linggo o papalapit sa 115 g/L, karaniwang binabawasan ang dosis sa halip na ihinto; maaari itong pansamantalang itigil kung lumampas sa 115 g/L. Ang pagtaas ng hemoglobin sa normal na saklaw gamit ang ESA ay hindi napatunayang nagpapabuti sa puso o bato at nauugnay sa mas maraming stroke at atake sa puso (CHOIR, TREAT). Ang layunin ay mapawi ang sintomas at maiwasan ang transfusion, hindi ang maabot ang "normal" na numero.Susihon kanunay ang hemoglobin ug gamita ang labing ubos nga epektibong dosis sa ESA. Ang KDIGO 2026 nagtambag batok sa paggamit sa ESA aron huptan ang hemoglobin sa 115 g/L o mas taas; kon mosaka ang hemoglobin og labaw sa 10 g/L sulod sa 2–4 ka semana o moduol sa 115 g/L, kasagaran kunhoran ang dosis imbes nga ihunong; mahimo kining ihunong sa makadiyot kon molapas sa 115 g/L. Ang pagpataas sa hemoglobin ngadto sa normal nga han-ay pinaagi sa ESA wala mapamatud-i nga makapaayo sa kasingkasing o kidney ug nalambigit sa mas daghang stroke ug atake sa kasingkasing (CHOIR, TREAT). Ang tumong mao ang paghupay sa sintomas ug paglikay sa transfusion, dili ang pagkab-ot sa "normal" nga numero. Regular a suriin ing hemoglobin at gamitan ing pekamababang epektibong dosis ning ESA. Magpayu ing KDIGO 2026 laban king pamangamit ning ESA para panatilian ing hemoglobin king 115 g/L o mas matas; nung tumaas ing hemoglobin lagpas 10 g/L king loob ning 2–4 lutu o papalapit ya king 115 g/L, karaniwang bawasan ing dosis kesa ihinto; malyari yang pansamantalang itigil nung lumampas ya king 115 g/L. Ing pagtaas ning hemoglobin king normal a saklaw gamit ing ESA ya ali mepatunayan a nagpapabuti king pusu o batu at me-link king mas dakal a stroke at atake king pusu (CHOIR, TREAT). Ing layunin ya mapawi ing sintomas at maiwasan ing transfusion, ali ing maabot ing "normal" a numeru.
ESA resistance — investigate before escalating dosePaglaban sa ESA — imbestigahan bago taasan ang dosisPagsukol sa ESA — imbestigahon sa wala pa taason ang dosis Paglaban king ESA — imbestigahan bago taasan ing dosis
If hemoglobin does not rise after 4–8 weeks despite adequate ESA dosing, do not simply increase the dose. Investigate: is iron truly adequate? Is there occult bleeding? Active infection or inflammation? Vitamin B12/folate deficiency? Hyperparathyroidism with marrow fibrosis? Anti-EPO antibodies (rare)? Each cause requires specific treatment, not more ESA.Kung ang hemoglobin ay hindi tumataas pagkatapos ng 4–8 linggo kahit may sapat na dosis ng ESA, huwag basta-basta taasan ang dosis. Imbestigahan: talaga bang sapat ang iron? May nakatagong pagdurugo? Aktibong impeksyon o pamamaga? Kakulangan ng Vitamin B12/folate? Hyperparathyroidism na may marrow fibrosis? Anti-EPO antibodies (bihira)? Ang bawat sanhi ay nangangailangan ng tiyak na paggamot, hindi mas maraming ESA.Kon ang hemoglobin dili mosaka human sa 4–8 ka semana bisan adunay igo nga dosis sa ESA, ayaw lang taason ang dosis. Imbestigahon: tinuod bang igo ang iron? Aduna bay naghisgot nga pagdugo? Aktibong impeksyon o pamamaga? Kakulang sa Vitamin B12/folate? Hyperparathyroidism nga adunay marrow fibrosis? Anti-EPO antibodies (panagsa)? Ang matag hinungdan nanginahanglan og espesipikong pagtambal, dili dugang ESA. Nung ing hemoglobin ya ali tumataas kapabanuan ning 4–8 lutu kahit atin sapat a dosis ning ESA, eka basta-basta taasan ing dosis. Imbestigahan: talaga bang sapat ing iron? Atin nakatagong pagdurugo? Aktibong impeksyon o pamamaga? Kakulangan ning Vitamin B12/folate? Hyperparathyroidism a atin marrow fibrosis? Anti-EPO antibodies (bihira)? Ing bawat sanhi ya nangangailangan ning tiyak a paggamut, ali mas dacal a ESA.
Eating for Healthy Blood — Iron-Rich Filipino FoodsPagkain para sa Malusog na Dugo — Mga Pagkaing May Mataas na Iron sa PilipinasPagkaon alang sa Malusog nga Dugo — Mga Pagkaon nga Dato sa Iron sa Pilipinas Pamangan para king Malusog a Daya — Deng Pagkaing Atin Matas a Iron king Pilipinas

This infographic highlights iron-rich Filipino foods such as malunggay, bangus, kangkong, mongo, and lean meat, shows what to avoid, and explains how a squeeze of calamansi can help your body absorb more iron.
Iron-rich foods — eat regularlyMga pagkaing mayaman sa iron — kainin nang regularMga pagkaon nga dato sa iron — kaonon nga regular Deng pagkaing mayaman king iron — kainin nang regular
- Lean beef and pork — heme iron (best absorbed, 15–35%)Manipis na baka at baboy — heme iron (pinakamadaling masipsip, 15–35%)Payat nga baka ug baboy — heme iron (labing madaling masuyop, 15–35%) Manipis a baka at baboy — heme iron (pinakamadaling masipsip, 15–35%)
- Chicken and turkey dark meatMadilim na karne ng manok at paboItom nga unod sa manok ug pabo Madilim a karne ning manok at pabo
- Malunggay (moringa) leaves — high non-heme iron; local and affordableDahon ng malunggay (moringa) — mataas na non-heme iron; lokal at abot-kayaDahon sa malunggay (moringa) — taas nga non-heme iron; lokal ug barato Dahon ning malunggay (moringa) — matas a non-heme iron; lokal at abot-kaya
- Mongo beans (mung beans) — plant-based ironMongo (mung beans) — iron mula sa halamanMongo (mung beans) — iron gikan sa tanum Mongo (mung beans) — iron mula king halaman
- Kangkong — moderate iron; boil to reduce potassium if neededKangkong — katamtamang iron; pakuluan upang mabawasan ang potassium kung kinakailanganKangkong — katamtamang iron; pabukalon aron mabawasan ang potassium kon kinahanglan Kangkong — katamtamang iron; pakuluan upang mabawasan ing potassium nung kinakailangan
- Fortified rice and cerealsFortified na bigas at cerealFortified nga bugas ug cereal Fortified a bigas at cereal
- Egg yolks — moderate iron contentPula ng itlog — katamtamang nilalaman ng ironPula sa itlog — katamtamang sulod sa iron Pula ning itlog — katamtamang nilalaman ning iron
- Bangus (milkfish) and other fishBangus at iba pang isdaBangus ug uban pang isda Bangus at iba pang isda
Reduce these — they block iron absorptionBawasan ito — humahadlang ang mga ito sa pagsipsip ng ironBawasan kini — nagpugong kini sa pagsuyop sa iron Bawasan ini — humahadlang ing deng ini king pagsipsip ning iron
- Tea and coffee within 1 hour of iron-rich meals (tannins)Tsaa at kape sa loob ng 1 oras pagkatapos ng mga pagkaing mayaman sa iron (tannins)Tsaa ug kape sulod sa 1 ka oras human sa mga pagkaon nga dato sa iron (tannins) Tsaa at kape king loob ning 1 oras kapabanuan ning deng pagkaing mayaman king iron (tannins)
- Calcium-rich foods (dairy) taken at the same time as iron supplementsMga pagkaing mayaman sa calcium (gatas) na kinukuha nang sabay sa mga iron supplementMga pagkaon nga dato sa calcium (gatas) nga gikuha nga dungan sa mga iron supplement Deng pagkaing mayaman king calcium (gatas) a kinukuha nang sabay king deng iron supplement
- Whole grain phytates when taken with iron supplementsMga phytate sa buong butil kapag kinuha kasama ang mga iron supplementMga phytate sa tibuok butil kon gikuha uban sa mga iron supplement Deng phytate king buong butil nung kinuha kasama ing deng iron supplement
- Antacids, phosphate binders taken simultaneously with oral ironMga antacid, phosphate binder na kinukuha nang sabay sa oral ironMga antacid, phosphate binder nga gikuha nga dungan sa oral iron Deng antacid, phosphate binder a kinukuha nang sabay king oral iron
- Excessive processed foods that lack nutritional densityLabis na mga processed na pagkain na kulang sa nutritional densitySobrang mga processed nga pagkaon nga kulang sa nutritional density Labis a deng processed a pamangan a kulang king nutritional density
Enhance iron absorption with vitamin CPalakasin ang pagsipsip ng iron gamit ang vitamin CPalig-ona ang pagsuyop sa iron gamit ang vitamin C Palakasin ing pagsipsip ning iron gamit ing vitamin C
Vitamin C (ascorbic acid) converts non-heme iron (from plants) from ferric (Fe³⁺) to ferrous (Fe²⁺) form — the absorbable form. Squeeze calamansi or dalandan over iron-rich plant foods at mealtime. A small amount of vitamin C (50–100 mg) with oral iron supplements can increase absorption by 2–4 fold. Do not exceed 1,000 mg vitamin C supplementation — high doses increase urinary oxalate and kidney stone risk.Ang Vitamin C (ascorbic acid) ay nagko-convert ng non-heme iron (mula sa mga halaman) mula sa ferric (Fe³⁺) patungong ferrous (Fe²⁺) — ang masisipsip na anyo. Pigain ang calamansi o dalandan sa mga pagkaing may iron mula sa halaman sa oras ng kain. Ang maliit na halaga ng vitamin C (50–100 mg) kasama ang mga oral iron supplement ay maaaring magpataas ng pagsipsip ng 2–4 beses. Huwag lagpasan ang 1,000 mg ng vitamin C supplementation — ang mataas na dosis ay nagpapataas ng urinary oxalate at panganib ng kidney stone.Ang Vitamin C (ascorbic acid) nagbag-o sa non-heme iron (gikan sa mga tanum) gikan sa ferric (Fe³⁺) ngadto sa ferrous (Fe²⁺) — ang masuyop nga porma. Puga og calamansi o dalandan sa mga pagkaon nga may iron gikan sa tanum sa oras sa pagkaon. Ang gamay nga kantidad sa vitamin C (50–100 mg) uban sa mga oral iron supplement mahimong makapataas sa pagsuyop og 2–4 ka pilo. Ayaw lapasa ang 1,000 mg nga vitamin C supplementation — ang taas nga dosis nagpataas sa urinary oxalate ug peligro sa kidney stone. Ing Vitamin C (ascorbic acid) ya nagko-convert ning non-heme iron (mula king deng halaman) mula king ferric (Fe³⁺) patungong ferrous (Fe²⁺) — ing masisipsip a anyo. Pigain ing calamansi o dalandan king deng pagkaing atin iron mula king halaman king oras ning kain. Ing maliit a halaga ning vitamin C (50–100 mg) kasama ing deng oral iron supplement ya maaaring magpataas ning pagsipsip ning 2–4 beses. Eka lagpasan ing 1,000 mg ning vitamin C supplementation — ing matas a dosis ya nagpapataas ning urinary oxalate at panganib ning kidney stone.
Iron Status Calculator — TSAT & Iron Deficiency ClassifierKalkulador ng Katayuan ng Iron — TSAT at Iron Deficiency ClassifierKalkulador sa Kahimtang sa Iron — TSAT ug Iron Deficiency Classifier Kalkulador ning Katayuan ning Iron — TSAT at Iron Deficiency Classifier
First choose your population — the thresholds are different for each. Then enter your iron panel to calculate TSAT and see how the numbers are interpreted. This tool evaluates and helps you discuss iron status with your doctor; it does not prescribe iron or decide the route (oral vs. IV) on its own. Interpretation follows KDIGO 2026.Piliin muna ang inyong populasyon — magkaiba ang mga threshold para sa bawat isa. Pagkatapos ilagay ang iron panel upang kalkulahin ang TSAT at makita kung paano binibigyang-kahulugan ang mga numero. Ang tool na ito ay sumusuri at tumutulong na talakayin ang katayuan ng iron sa inyong doktor; hindi ito nagrereseta ng iron o nagpapasya ng ruta (oral vs. IV) nang mag-isa. Sumusunod sa KDIGO 2026 ang interpretasyon.Pilia una ang inyong populasyon — lahi ang mga threshold sa matag usa. Dayon isulod ang iron panel aron makalkula ang TSAT ug makita giunsa paghubad ang mga numero. Kini nga himan nag-evaluate ug motabang nga hisgotan ang kahimtang sa iron uban sa inyong doktor; kini dili mag-reseta og iron o magdesisyon sa ruta (oral vs. IV) sa iyang kaugalingon. Ang paghubad nagsunod sa KDIGO 2026. Piliin mumuna ing inyu populasyon — miyayaliwa ing deng threshold para king balang metung. Kaibat ilagay ing iron panel para kalkulahin ing TSAT at akit nung makananu bibiyang-kahulugan ing deng numeru. Ing tool a ini ya sumusuri at saup a talakayan ing katayuan ning iron kayabe ing inyu doktor; ali ne magreseta ning iron o magpasya king ruta (oral vs. IV) mag-isa. Ing interpretasyon ya tutuki king KDIGO 2026.
⚕ TSAT = (Serum Iron ÷ TIBC) × 100. Ferritin is an acute phase reactant — elevated by inflammation, infection, or malignancy independent of iron stores. Classification per KDIGO 2026. This tool is for educational guidance only — iron therapy decisions require physician assessment.
Treatment Targets for CKD-Related AnemiaMga Target sa Paggamot ng Anemia na Kaugnay sa CKDMga Target sa Pagtambal sa Anemia nga May Kalabotan sa CKD Deng Target king Paggamut ning Anemia a Kaugnay king CKD
Your kidney team checks why hemoglobin (Hb) is low before changing treatment. Iron tests and symptoms matter together. IV iron is usually preferred in hemodialysis; oral or IV iron can be chosen in non-dialysis CKD and peritoneal dialysis.
For adults taking an erythropoiesis-stimulating agent (ESA/EPO), the Hb goal is individualized and below 11.5 g/dL (115 g/L). More EPO is not a treatment for every cause of fatigue. Do not change your dose yourself.
The team usually withholds routine iron if ferritin is >700 ng/mL or TSAT ≥40%, and considers pausing it during systemic infection. These are treatment-review limits, not tests that prove iron overload.
Sinusuri ng kidney team ang sanhi ng mababang hemoglobin (Hb) bago baguhin ang gamutan. Magkasamang isinasaalang-alang ang iron tests at sintomas. Karaniwang mas pinipili ang IV iron sa hemodialysis; maaaring oral o IV iron sa CKD na hindi naka-dialysis at sa peritoneal dialysis.
Para sa adult na gumagamit ng erythropoiesis-stimulating agent (ESA/EPO), ang layunin sa Hb ay indibidwal at mas mababa sa 11.5 g/dL (115 g/L). Hindi dagdag na EPO ang lunas sa lahat ng sanhi ng pagod. Huwag baguhin ang dosis nang sarili lamang.
Karaniwang ipinagpapaliban ang regular na iron kung ferritin >700 ng/mL o TSAT ≥40%; maaaring pansamantalang ihinto ito habang may systemic infection. Hindi sapat ang mga numerong ito upang patunayang may iron overload.
Susihon sa kidney team ang hinungdan sa ubos nga hemoglobin (Hb) sa dili pa usbon ang tambal. Tan-awon ang iron tests uban sa mga sintomas. Kasagarang mas pilion ang IV iron sa hemodialysis; mahimong oral o IV iron sa CKD nga wala mag-dialysis ug sa peritoneal dialysis.
Sa hamtong nga naggamit og erythropoiesis-stimulating agent (ESA/EPO), ang tumong sa Hb ipahaom sa pasyente ug ubos sa 11.5 g/dL (115 g/L). Dili dugang EPO ang tubag sa tanang hinungdan sa kakapoy. Ayaw usba ang dosis sa imong kaugalingon.
Kasagarang dili ihatag ang regular nga iron kon ferritin >700 ng/mL o TSAT ≥40%; mahimong ihunong kini sa makadiyot panahon sa systemic infection. Kini nga mga numero dili igo nga pamatuod sa iron overload.
Suriin na ning kidney team ing sangkan ning mababang hemoglobin (Hb) bayu baguan ing gamutan. Lawan la deng iron tests kayabe deng sintomas. Karaniwang mas pipilinan ing IV iron king hemodialysis; malyaring oral o IV iron king CKD a e pa maki-dialysis at king peritoneal dialysis.
Para king adult a gagamit erythropoiesis-stimulating agent (ESA/EPO), ing layunin king Hb ya me-personalize at mas mababa king 11.5 g/dL (115 g/L). Ali dagdag a EPO ing lunas king anggang sangkan ning kapagalan. E mu baguan ing dosis nang sarili mu.
Karaniwang ipagpaliban ing regular a iron nung ferritin >700 ng/mL o TSAT ≥40%; malyari yang pansamantalang itigil kabang atin systemic infection. E sapat deng numerung ini para patunayan ing iron overload.
Clinician reference: population-specific KDIGO 2026 criteria
Fatigue & Kidney-Specific Quality of Life AssessmentsPagtatasa ng Pagod at Kalidad ng Buhay sa BatoPagtimbang sa Pagod ug Kalidad sa Kinabuhi alang sa BatoPagsusuri ning Kapagalan at Kalidad ning Biyay para king Bato
Anemia in CKD significantly impacts how you feel and your quality of life. Use these validated tools to track fatigue severity and kidney-related quality of life — share results with your nephrologist.Ang anemia sa CKD ay malaki ang epekto sa inyong pakiramdam at kalidad ng buhay. Gamitin ang mga tool na ito upang subaybayan ang pagod at kalidad ng buhay.Ang anemia sa CKD grabe ang epekto sa imong gibati ug kalidad sa kinabuhi. Gamiton kining mga himan aron subaybayan ang pagod.Ing anemia king CKD malaki ing epekto keng inyu pakiramdam at kalidad ning biyay. Gamitin dening kasangkapan para subaybayan ing kapagalan.
For each statement, select how true it has been for you during the past 7 days. 0 = Not at all, 1 = A little bit, 2 = Somewhat, 3 = Quite a bit, 4 = Very much.Para sa bawat pahayag, piliin kung gaano ito katotoo para sa inyo sa nakalipas na 7 araw.Alang sa matag pahayag, pilia kung unsa kadako kini tinuod para kanimo sa miaging 7 ka adlaw.Para king balang salita, pili kung magkanu ining tutuo para kenu king nakalipas a 7 aldaw.
⚕ FACIT-Fatigue: Yellen et al. (1997), validated for CKD/dialysis. KDQOL-36: Ware et al., kidney-targeted QoL (quality of life) instrument. Educational tools only — results do not replace clinical evaluation. Share with your nephrologist for discussion.⚕ Mga kagamitang pang-edukasyon lamang; hindi pumapalit sa pagtatasa ng doktor.⚕ Mga himan sa edukasyon lamang; dili makapuli sa pagtimbang sa doktor.⚕ Deng kasangkapang pang-edukasyon lamang; e kalagan ing pagsusuri ning doktor.